You’re cruising through a micro Q-bank and you hit a “white discharge” vignette. Easy—Candida albicans, right? But Step-style questions aren’t testing whether you recognize Candida once. They’re testing whether you can defend it against five plausible distractors and use the stem details to exclude everything else. This post breaks down a classic Candida vignette the way you should on test day: correct answer first, then why every other option is wrong (and what would make it right).
Tag: Microbiology > Mycology & Parasitology
The Vignette (Classic Step Style)
A 28-year-old woman presents with intense vulvovaginal pruritus and thick, white “cottage cheese” discharge for 3 days. She recently completed a 10-day course of amoxicillin-clavulanate for sinusitis. Vaginal pH is 4.2. Wet mount shows budding yeast with pseudohyphae.
Most likely organism?
A. Candida albicans
B. Gardnerella vaginalis
C. Trichomonas vaginalis
D. Chlamydia trachomatis
E. Aspergillus fumigatus
Correct Answer: Candida albicans
Why it’s Candida (Anchor the stem)
This stem basically hands you the diagnosis:
- Symptoms: pruritus + thick, clumpy white discharge (often described as “cottage cheese”)
- Risk factor: recent antibiotics → decreased normal vaginal flora → yeast overgrowth
- pH: normal/acidic (≤ 4.5) points away from BV and Trichomonas
- Microscopy: budding yeast + pseudohyphae = Candida
High-yield Candida albicans facts (USMLE-ready)
What you should instantly associate:
- Morphology
- Budding yeast and pseudohyphae
- Germ tubes positive (classically C. albicans and C. dubliniensis)
- Common presentations
- Vulvovaginitis (pruritus, thick discharge, normal pH)
- Oral thrush (creamy white plaques that scrape off)
- Esophagitis in AIDS (odynophagia; linear plaques)
- Candidemia in hospitalized pts (lines, TPN, neutropenia)
- Risk factors
- Antibiotics, diabetes, pregnancy, immunosuppression, neutropenia, indwelling catheters
- Treatment patterns
- Vulvovaginal: topical azoles or fluconazole
- Esophagitis/systemic: fluconazole or echinocandin (esp. severe/ICU)
Why Each Distractor Is Wrong (and How to Recognize It When It’s Right)
B. Gardnerella vaginalis — Bacterial vaginosis (BV)
Why it’s wrong here:
- BV usually has thin, gray/white discharge—not thick “cottage cheese”
- Fishy odor is classic (esp after KOH “whiff test”)
- pH is elevated (> 4.5), not normal/acidic
- Wet mount: clue cells (epithelial cells coated with bacteria), not budding yeast/pseudohyphae
When it would be right:
- Discharge + odor + pH > 4.5 + clue cells
High-yield association
- BV is not an “infection” with inflammation like Candida/Trich: less pruritus, more odor/discharge
- Treatment: metronidazole or clindamycin
C. Trichomonas vaginalis — Motile protozoan STI
Why it’s wrong here:
- Trich causes frothy, yellow-green discharge
- Strawberry cervix (punctate hemorrhages) is classic
- pH is elevated (> 4.5)
- Wet mount: motile, flagellated trophozoites (not yeast)
When it would be right:
- Frothy discharge + strawberry cervix + pH > 4.5 + motile organisms
High-yield association
- Treat patient and partners: metronidazole or tinidazole
- Trich is a protozoan (not a fungus), but it lives in the same Step neighborhood as BV/Candida because it’s a common vaginitis differential.
D. Chlamydia trachomatis — Cervicitis/PID, not vaginitis
Why it’s wrong here:
- Chlamydia typically causes mucopurulent cervicitis and/or urethritis
- Symptoms are often minimal; discharge isn’t classically thick and white
- Microscopy in the stem shows yeast forms—Chlamydia is obligate intracellular, not seen as budding yeast/pseudohyphae on wet mount
- Vaginal pH isn’t the key discriminator for cervicitis the way it is for vaginitis
When it would be right:
- Postcoital bleeding, mucopurulent discharge, cervical friability, PID signs, NAAT positive
- Neonate: conjunctivitis or pneumonia (afebrile)
High-yield association
- No peptidoglycan → beta-lactams don’t work
- Treat: doxycycline (or azithro in pregnancy); treat partners
E. Aspergillus fumigatus — Opportunistic mold, not “vaginal yeast infection”
Why it’s wrong here:
- Aspergillus is an environmental mold, classically pulmonary disease in immunocompromised pts—not vulvovaginitis
- Morphology: septate hyphae with acute-angle (~45°) branching, not budding yeast/pseudohyphae
- Clinical pictures: allergic bronchopulmonary aspergillosis, aspergilloma, invasive aspergillosis
When it would be right:
- Neutropenic or transplant patient with fever, pleuritic chest pain, hemoptysis; CT with nodules/halo sign
- Histology showing acute-angle branching septate hyphae
High-yield association
- Treatment: voriconazole (invasive)
- Can also use amphotericin B, isavuconazole depending on scenario
The Real Test-Taking Skill: Use “Triads” to Separate Vaginitis Causes
Here’s the highest-yield way to sort Candida vs BV vs Trich quickly:
| Feature | Candida | BV (Gardnerella & anaerobes) | Trichomonas |
|---|---|---|---|
| Discharge | Thick, white, clumpy | Thin, gray/white | Frothy, yellow-green |
| Pruritus | Prominent | Minimal | Common |
| Odor | Usually none | Fishy (whiff +) | Often malodorous |
| Vaginal pH | Normal (≤ 4.5) | High (> 4.5) | High (> 4.5) |
| Microscopy | Budding yeast, pseudohyphae | Clue cells | Motile flagellates |
| Treatment | Fluconazole / topical azole | Metronidazole | Metronidazole + treat partners |
Key move: If the stem gives you pH and wet mount, you’re expected to use them.
Extra High-Yield Candida Pearls (Often Tested as Second-Order Details)
1) Thrush vs Leukoplakia (common trap)
- Thrush (Candida): white plaques that scrape off (may bleed)
- Oral hairy leukoplakia (EBV): white plaques that do not scrape off (often lateral tongue, AIDS)
2) Candida esophagitis vs HSV/CMV esophagitis (Step 2 favorite)
| Pathogen | Typical patient | Endoscopy clue | Symptom |
|---|---|---|---|
| Candida | AIDS, steroids | White plaques | Odynophagia |
| HSV | Transplant, immunosuppressed | “Volcano” ulcers | Odynophagia |
| CMV | Advanced immunosuppression | Large linear ulcers | Odynophagia |
3) Candidemia risk factors (ICU classic)
Think: lines + sugar + neutropenia
- Central venous catheter
- TPN
- Broad-spectrum antibiotics
- Neutropenia/chemo
Treatment often starts with an echinocandin (e.g., caspofungin) in sick hospitalized patients until speciation/susceptibilities return.
How to Answer These Questions Like a Top Scorer
- Name the syndrome first (vaginitis)
- Use pH + discharge description to narrow to Candida/BV/Trich
- Use wet mount to confirm
- Only then look at the organism choices—and actively rule out each distractor
If you can explain why each wrong option is wrong, you’re not just memorizing—you’re building the test-day reflex that turns “easy questions” into guaranteed points.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
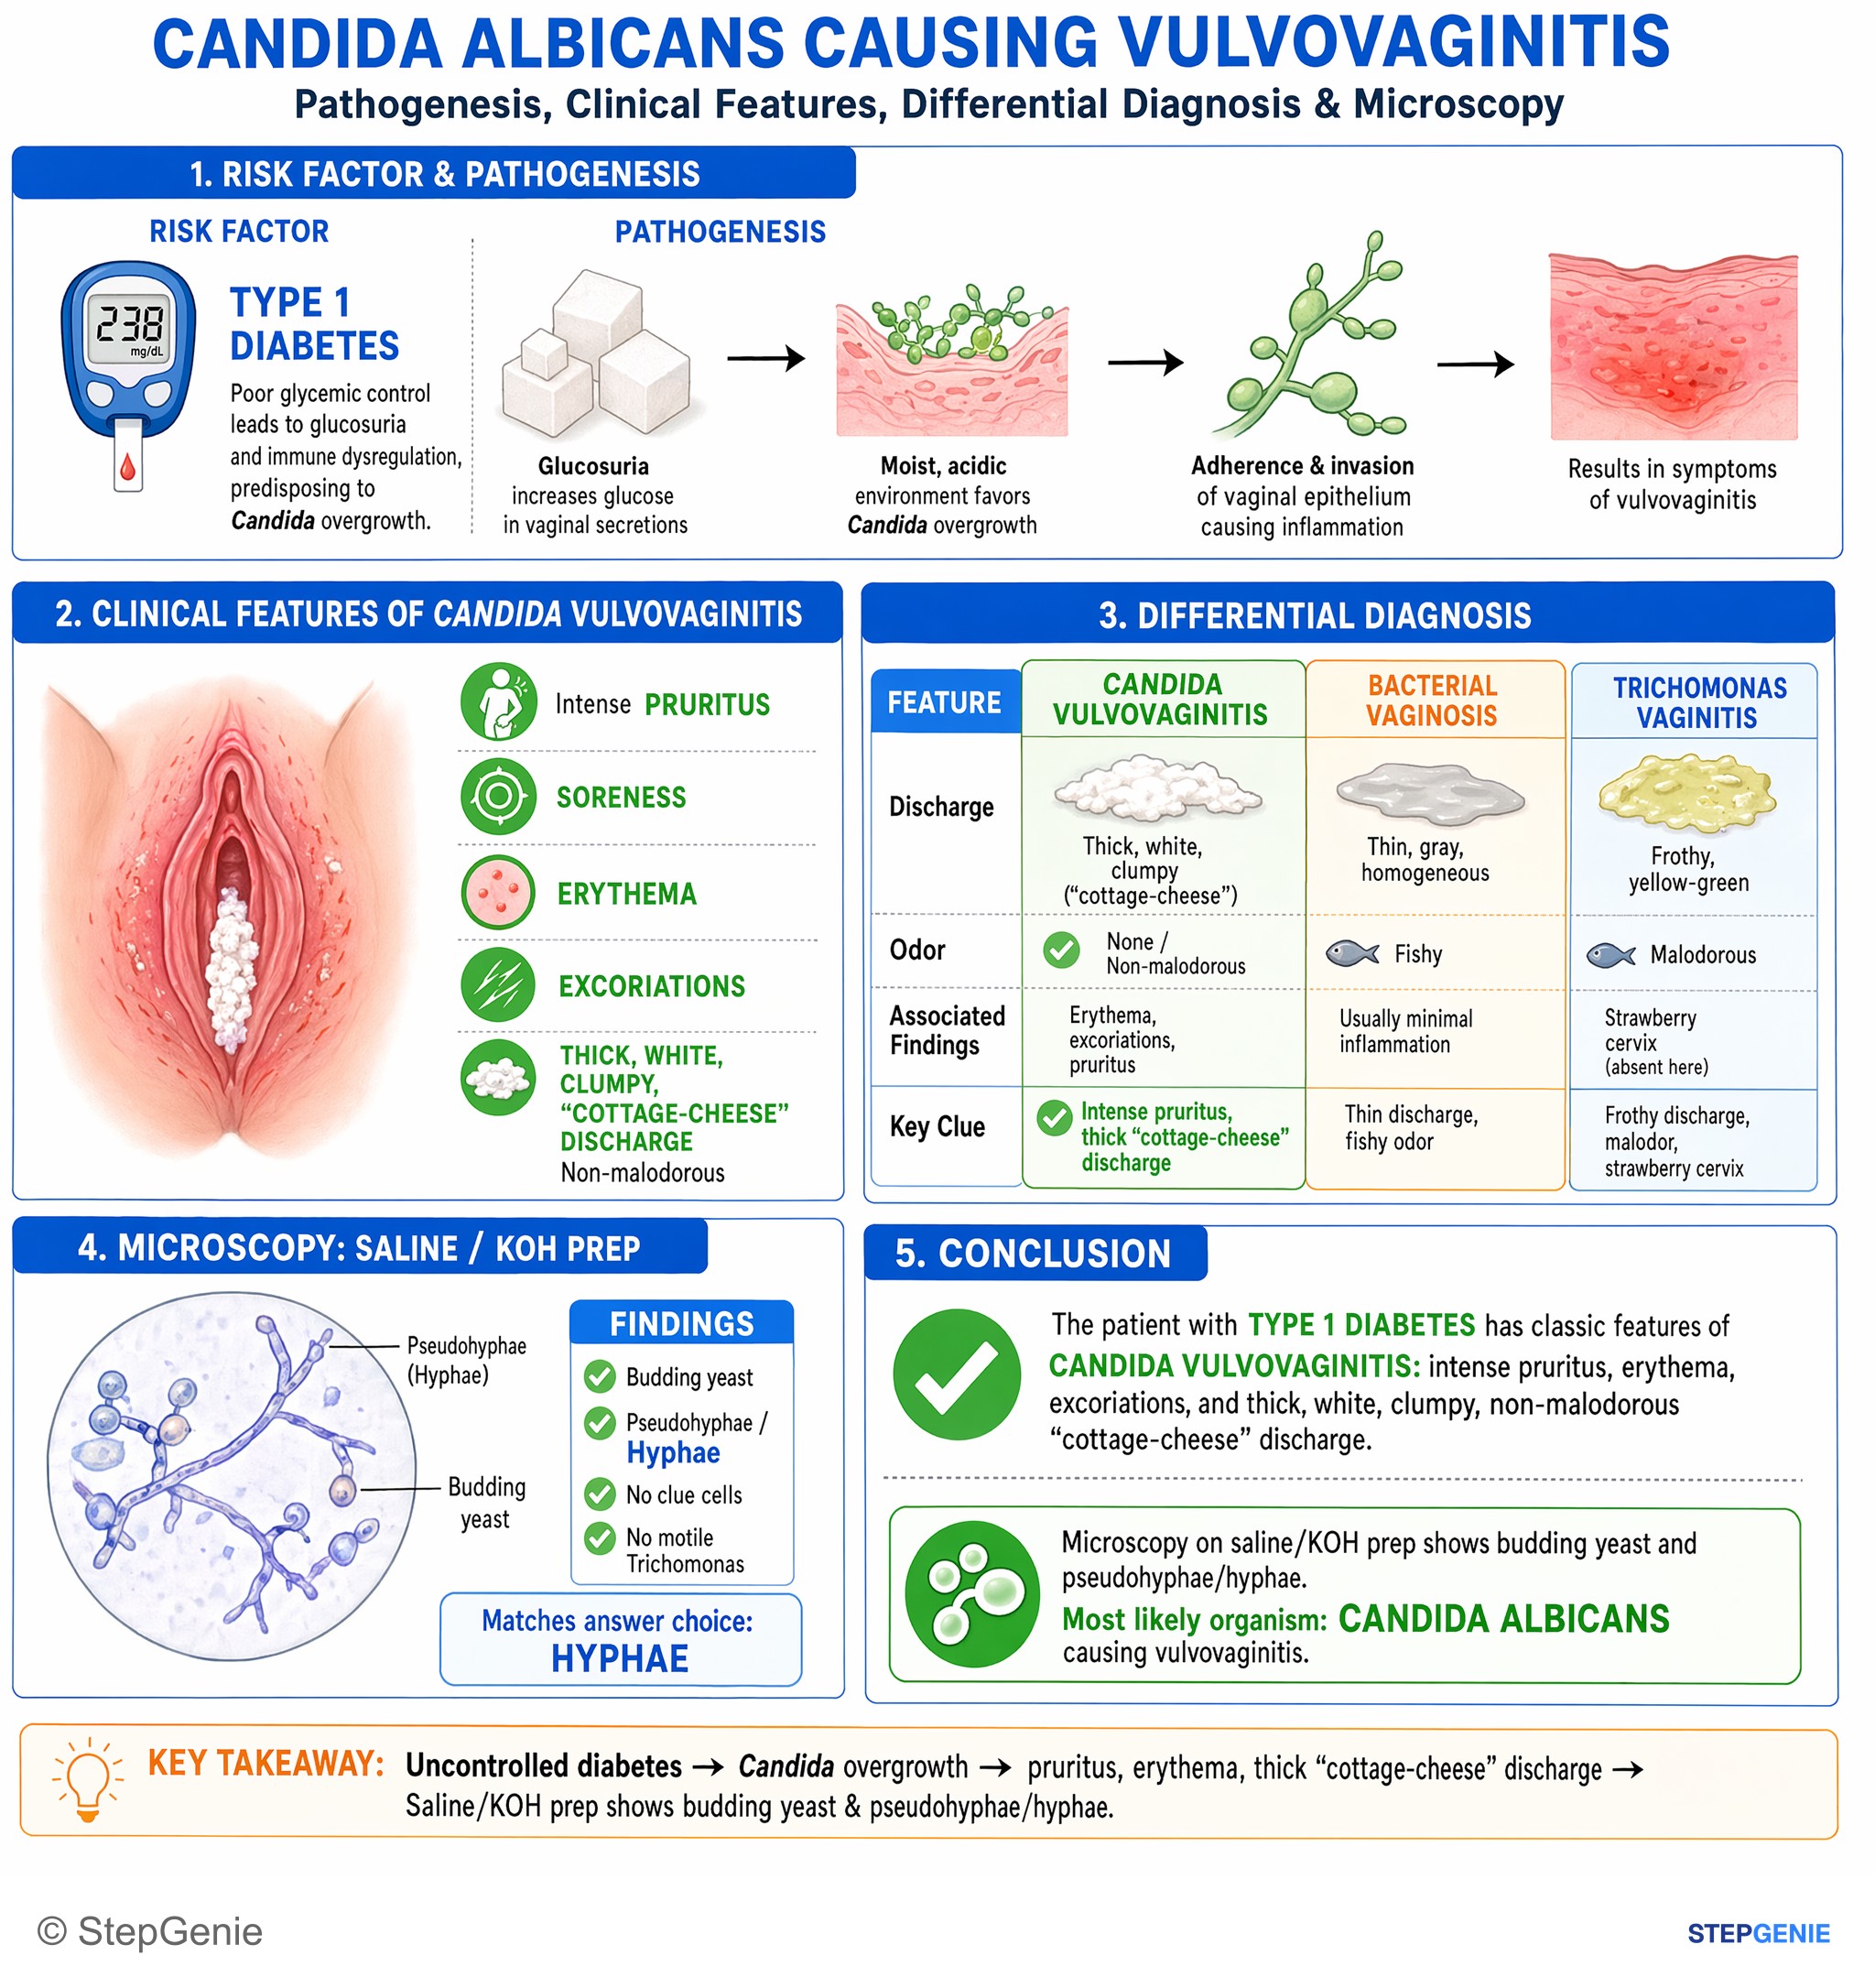
Candida vulvovaginitis from uncontrolled diabetes: pruritus, erythema, thick “cottage-cheese” discharge; saline or KOH prep shows budding…
USMLE Step 1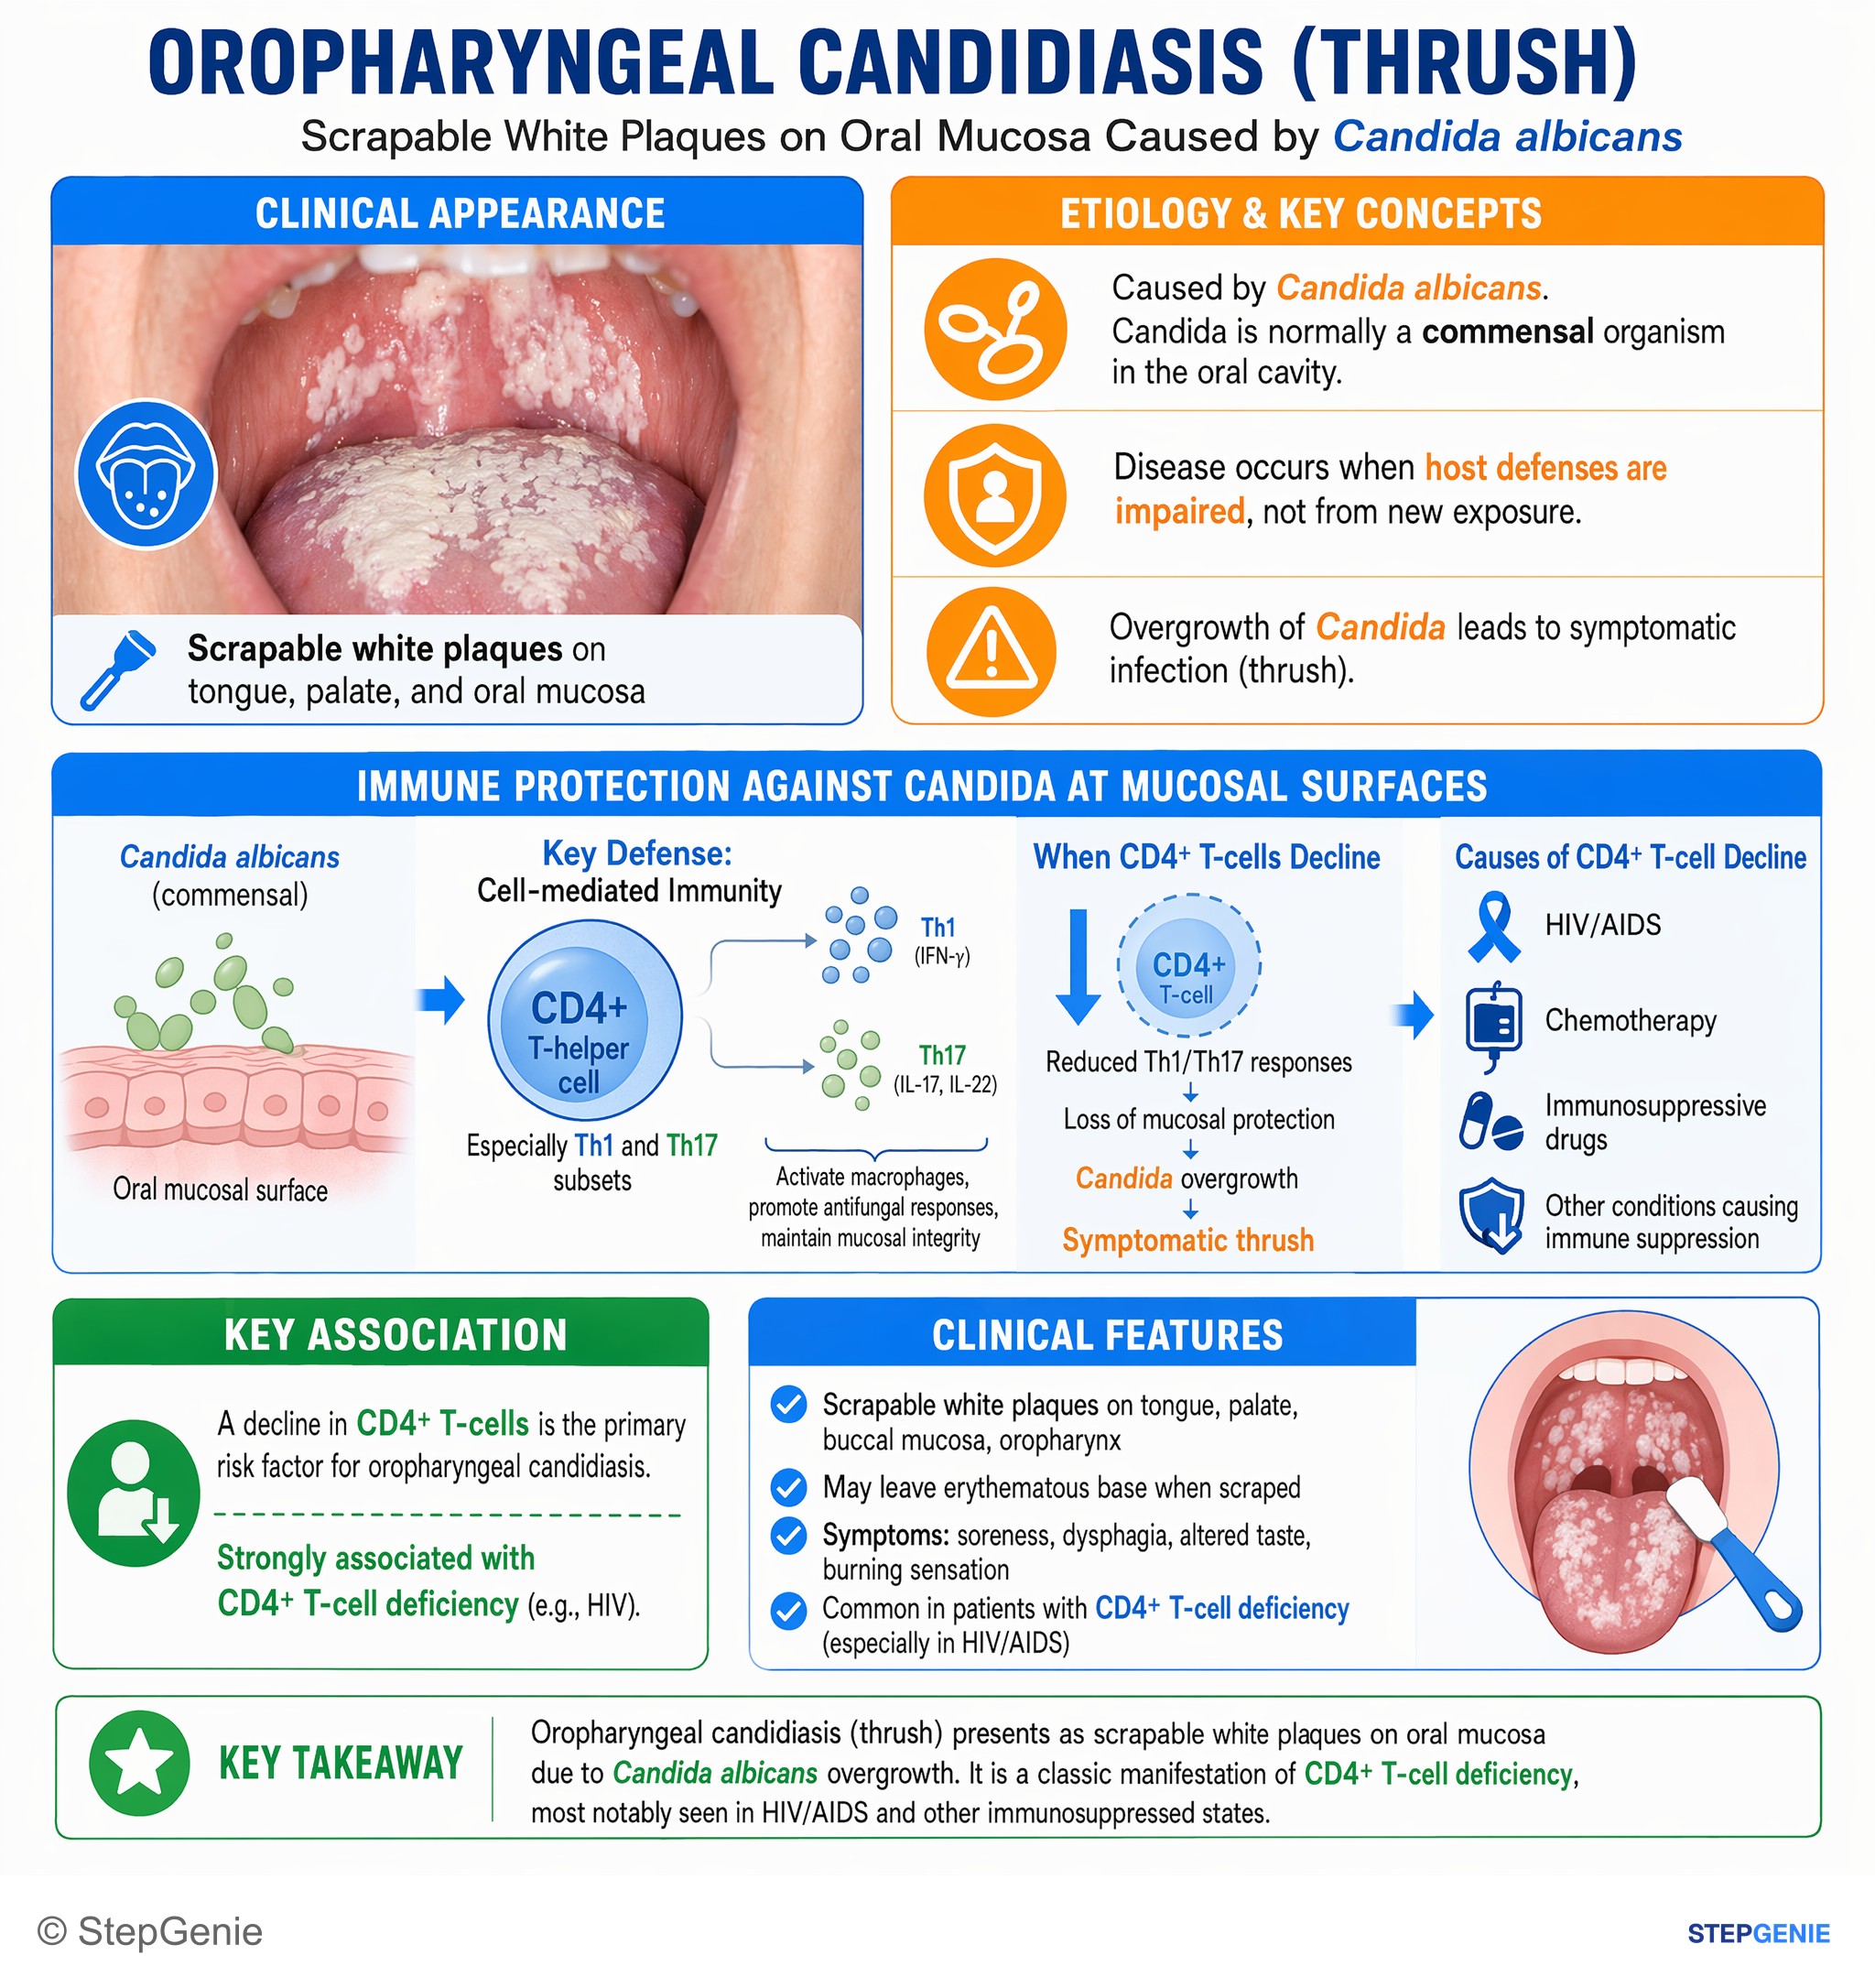
Oropharyngeal candidiasis (thrush) presents as scrapable white plaques on tongue/palate and is strongly associated with CD4+ T-cell…
USMLE Step 1Frequently Asked Questions
How do you tell Candida vaginitis from bacterial vaginosis and Trichomonas on a question stem?
Candida is identified by thick white clumpy discharge, prominent pruritus, a normal or acidic vaginal pH of 4.5 or less, and wet mount showing budding yeast with pseudohyphae. Bacterial vaginosis instead causes thin gray-white discharge, a fishy odor, elevated pH, and clue cells. Trichomonas causes frothy yellow-green discharge, elevated pH, and motile flagellated trophozoites, often with a strawberry cervix.
Why do recent antibiotics make Candida albicans more likely?
Recent antibiotics make Candida more likely because they decrease the normal vaginal flora and allow yeast overgrowth. In a patient with intense vulvovaginal pruritus and thick white cottage cheese discharge after a course of amoxicillin-clavulanate, that risk factor strongly supports Candida albicans. The diagnosis is reinforced further if vaginal pH stays normal or acidic and microscopy shows budding yeast with pseudohyphae.
What wet mount finding points to Candida albicans?
Budding yeast with pseudohyphae on wet mount points to Candida albicans. That microscopy finding is a classic discriminator when the differential includes other common causes of vaginitis. Gardnerella vaginalis shows clue cells rather than yeast forms, and Trichomonas vaginalis shows motile flagellated trophozoites. If the stem gives both pH and wet mount, those details are meant to be used together to separate these diagnoses.
What is the usual treatment for vulvovaginal Candida albicans infection?
Vulvovaginal Candida albicans is usually treated with topical azoles or fluconazole. The classic presentation is intense pruritus with thick white discharge, normal vaginal pH, and budding yeast with pseudohyphae on wet mount. More severe esophageal or systemic Candida infections are treated with fluconazole or an echinocandin, especially in severe or ICU settings.
Why is Chlamydia trachomatis not the best answer for a thick white vaginal discharge vignette?
Chlamydia trachomatis is not the best answer because it usually causes mucopurulent cervicitis or urethritis rather than classic vaginitis. Its symptoms are often minimal, and the discharge is not typically thick and white. A wet mount showing budding yeast with pseudohyphae points away from Chlamydia, which is obligate intracellular and would not appear as yeast forms on this type of microscopy.