The dermatophytes are three genera of keratin-eating molds: M.E.T., for Microsporum, Epidermophyton and Trichophyton. They live only on keratin, so they infect skin, hair and nails and rarely invade deeper. Microsporum takes hair and skin, Epidermophyton skin and nails but not hair, and Trichophyton all three. A KOH prep shows septate, branching hyphae. Skin infections get topical antifungals, while hair (tinea capitis) needs oral therapy and nails (onychomycosis) usually do: terbinafine for most, with griseofulvin preferred for Microsporum scalp infections in children.
The core mnemonic: "M.E.T. eats keratin"
- Microsporum
- Epidermophyton
- Trichophyton
One-liner: M.E.T. eats keratin. The dermatophytes are Microsporum, Epidermophyton and Trichophyton, and they need keratin (stratum corneum, hair, nails) to survive.
Visual hook: picture a subway turnstile labeled "M.E.T." A commuter walks up carrying a giant bag marked KERATIN (skin, hair, nails). The M.E.T. gate lets through only keratin, just as dermatophytes stay in keratinized tissue.
Which genus infects what
| Genus | Skin | Hair | Nails | Classic clue |
|---|---|---|---|---|
| Microsporum | Yes | Yes | No | M. canis (from cats and dogs) and M. audouinii fluoresce blue-green under a Wood lamp |
| Epidermophyton | Yes | No | Yes | Epidermis and nails only |
| Trichophyton | Yes | Yes | Yes | T. rubrum is the most common cause of tinea corporis; T. tonsurans causes most US tinea capitis and does not fluoresce |
Mini-mnemonics inside the mnemonic:
- Epidermophyton = Epidermis + nails, no hair.
- Microsporum = M for "Many hairs": hair and skin, not nails.
- Trichophyton = triple threat: skin, hair and nails.
Tinea by site
| Infection | Site | Stem clues | First-line treatment |
|---|---|---|---|
| Tinea corporis ("ringworm") | Body | Pink-red annular plaques with a raised, scaly border that expands outward and clears centrally | Topical azole or terbinafine twice daily until 7–10 days after the rash clears (about 2–3 weeks); oral itraconazole or terbinafine if extensive |
| Tinea cruris ("jock itch") | Groin | Scrotum usually spared | Topical |
| Tinea pedis ("athlete's foot") | Feet | Scaling and erosion between the toes, a moccasin pattern on the soles, or vesicles and bullae | Topical; oral for severe moccasin-type or extensive disease |
| Tinea capitis | Scalp hair, mainly children | Scaling, patchy hair loss, black dots (hairs broken at the scalp), or a kerion (boggy, inflamed mass) | Oral (terbinafine for Trichophyton, griseofulvin for Microsporum) plus selenium sulfide 2.5% shampoo |
| Onychomycosis (tinea unguium) | Nails | Thickened, yellow nails with debris beneath; commonly T. rubrum | Confirm first; oral terbinafine 250 mg daily for 6 weeks (fingernails) or 12 weeks (toenails) |
Scalp patterns: T. tonsurans grows inside the hair shaft (endothrix), so hairs break at the scalp surface, giving black dot tinea. M. audouinii breaks hairs above the surface, giving gray patch tinea. Children may attend school during treatment. For a severely inflamed lesion or kerion, Merck adds a short tapering course of prednisone to the oral antifungal.
Diagnosis: what they keep asking about
- KOH prep: KOH dissolves the skin cells and leaves fungal elements intact; dermatophytes show septate, branching hyphae of even width, sometimes with chains of rectangular arthrospores. Use skin scrapings, or plucked hairs for tinea capitis.
- Fungal culture: the gold standard for naming the organism (often on Sabouraud dextrose agar); needed mainly for scalp and nail infections.
- Wood lamp: only some species fluoresce (blue-green with M. canis and M. audouinii). Most dermatophytes seen in the United States, including T. tonsurans, do not, so a negative Wood lamp never rules out tinea.
- Onychomycosis: confirm a fungal cause (KOH, culture, PAS stain of clippings or PCR) before starting oral therapy, because other nail diseases look the same.
- PCR is required to confirm the emerging, terbinafine-resistant Trichophyton indotineae.
Treatment and how the drugs work
| Drug | Mechanism | High-yield facts |
|---|---|---|
| Terbinafine (topical or oral) | Inhibits squalene epoxidase; squalene builds up and kills the fungus | First-line oral drug for onychomycosis and Trichophyton tinea capitis; check transaminases before starting (rare liver failure); taste disturbance; inhibits CYP2D6 |
| Azoles (clotrimazole, miconazole, econazole topically; itraconazole orally) | Inhibit lanosterol 14-alpha-demethylase, blocking ergosterol synthesis | Topicals for skin; oral itraconazole for extensive or resistant disease |
| Griseofulvin (oral) | Microtubule assembly inhibitor: disrupts the mitotic spindle; binds newly formed keratin | Preferred for Microsporum tinea capitis; take with a high-fat meal; avoid in pregnancy, porphyria and liver failure; induces CYP450 (weakens warfarin); photosensitivity |
Rule of thumb: if it is in the hair follicle or nail plate, think systemic. Oral drugs are used for most scalp and nail infections; for nails, the newer topicals efinaconazole and tavaborole penetrate the nail better than older agents such as ciclopirox, but oral terbinafine is preferred. Griseofulvin is a classic CYP450 inducer, and terbinafine inhibits CYP2D6; review both in this CYP450 inducers and inhibitors guide.
Look-alikes and complications
- Tinea versicolor is not a dermatophyte infection: Malassezia furfur causes scaly, hypo- or hyperpigmented patches on the trunk, and KOH shows "spaghetti and meatballs" (hyphae plus budding yeast). Treat with selenium sulfide or topical azoles, or oral fluconazole if extensive.
- Candidal intertrigo vs tinea cruris: Candida involves the scrotum, has satellite lesions and is uniformly red without central clearing. Compare the yeast in this Candida albicans 5-second rule.
- Tinea incognito: tinea modified by topical steroids, so it looks atypical. Avoid combination steroid-antifungal creams such as betamethasone/clotrimazole, which can aggravate the infection; high-potency steroid combinations are a likely driver of resistance.
- Dermatophytid (id) reaction: a secondary rash, often on the hands or fingers, in someone with tinea pedis.
- Cellulitis and lymphangitis: tinea pedis cracks the skin and lets bacteria in.
- Majocchi granuloma: a deep follicular tinea, usually on the legs.
- Emerging strains: Trichophyton indotineae causes extensive, intensely itchy, highly contagious tinea corporis, cruris and faciei. It emerged in India (first clinical cases described after 2014), was first reported in the United States in 2023, is often resistant to terbinafine through squalene epoxidase gene mutations, and oral itraconazole is the drug of choice. T. mentagrophytes genotype VII has caused sexually transmitted genital, anal and oral tinea.
Exam traps
- Microsporum and nails: it infects hair and skin, not nails; Epidermophyton infects skin and nails, not hair.
- Negative Wood lamp: does not exclude tinea capitis, because T. tonsurans, the most common US cause, does not fluoresce.
- Topical therapy alone for tinea capitis: wrong; topicals only reduce spread. For most onychomycosis, oral terbinafine is preferred; topicals suit mild disease with few nails.
- Oral terbinafine for a toenail before confirming fungus: wrong; confirm first.
- Griseofulvin in pregnancy: contraindicated (fetal abnormalities).
- Tinea versicolor listed as a dermatophyte: wrong; it is Malassezia.
- Rash involving the scrotum with satellite papules: think Candida, not tinea cruris.
Worked example
Vignette. A 6-year-old boy has an itchy, scaly, round patch of hair loss on his scalp with broken hairs. The family adopted a kitten 2 months ago. Under a Wood lamp, the affected hairs fluoresce blue-green. A KOH prep of plucked hairs shows septate hyphae. What is the most appropriate treatment?
Answer: Oral griseofulvin (taken with a fatty meal), plus selenium sulfide 2.5% shampoo to reduce spread.
Why the tempting distractors are wrong:
- Topical clotrimazole alone: topicals are not sufficient as monotherapy for tinea capitis; they only help reduce spread.
- Betamethasone/clotrimazole cream: combination steroid products can aggravate fungal infections.
- Oral terbinafine: a first-line choice for Trichophyton, but griseofulvin is preferred in children when the cause is Microsporum, and blue-green fluorescence after exposure to a kitten points to M. canis.
- Keep him home from school until cured: children may attend school during treatment.
Key takeaways (flashcard summary)
- Dermatophytes = M.E.T.: Microsporum, Epidermophyton, Trichophyton; they eat keratin (skin, hair, nails).
- Epidermophyton: no hair. Microsporum: no nails. Trichophyton: all three.
- Dx: KOH shows septate, branching hyphae; culture names the species; Wood lamp is positive mainly with some Microsporum species (blue-green).
- Tx: topical for skin; oral for hair and most nail infections (terbinafine; griseofulvin for Microsporum in children); confirm onychomycosis first.
- Drugs: terbinafine blocks squalene epoxidase; azoles block lanosterol 14-alpha-demethylase; griseofulvin blocks microtubules and induces CYP450.
- New threat: terbinafine-resistant T. indotineae; treat with itraconazole.
Sources
- Overview of Dermatophytoses — Merck Manual Professional Edition
- Tinea Capitis — Merck Manual Professional Edition
- Tinea Corporis — Merck Manual Professional Edition
- Tinea Pedis — Merck Manual Professional Edition
- Tinea Versicolor — Merck Manual Professional Edition
- Onychomycosis — Merck Manual Professional Edition
- Ely JW, Rosenfeld S, Seabury Stone M. Diagnosis and Management of Tinea Infections — American Family Physician (2014)
- Hainer BL. Dermatophyte Infections — American Family Physician (2003)
- Hill RC, et al. Expert Panel Review of Skin and Hair Dermatophytoses in an Era of Antifungal Resistance — American Journal of Clinical Dermatology (2024), via CDC Stacks
- Reiss E, DiSalvo A. Superficial Mycoses — Microbiology and Immunology On-line
- Terbinafine Tablets — FDA Prescribing Information (DailyMed)
- Griseofulvin Tablets — FDA Prescribing Information (DailyMed)
- Antifungal Medications — Merck Manual Professional Edition
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
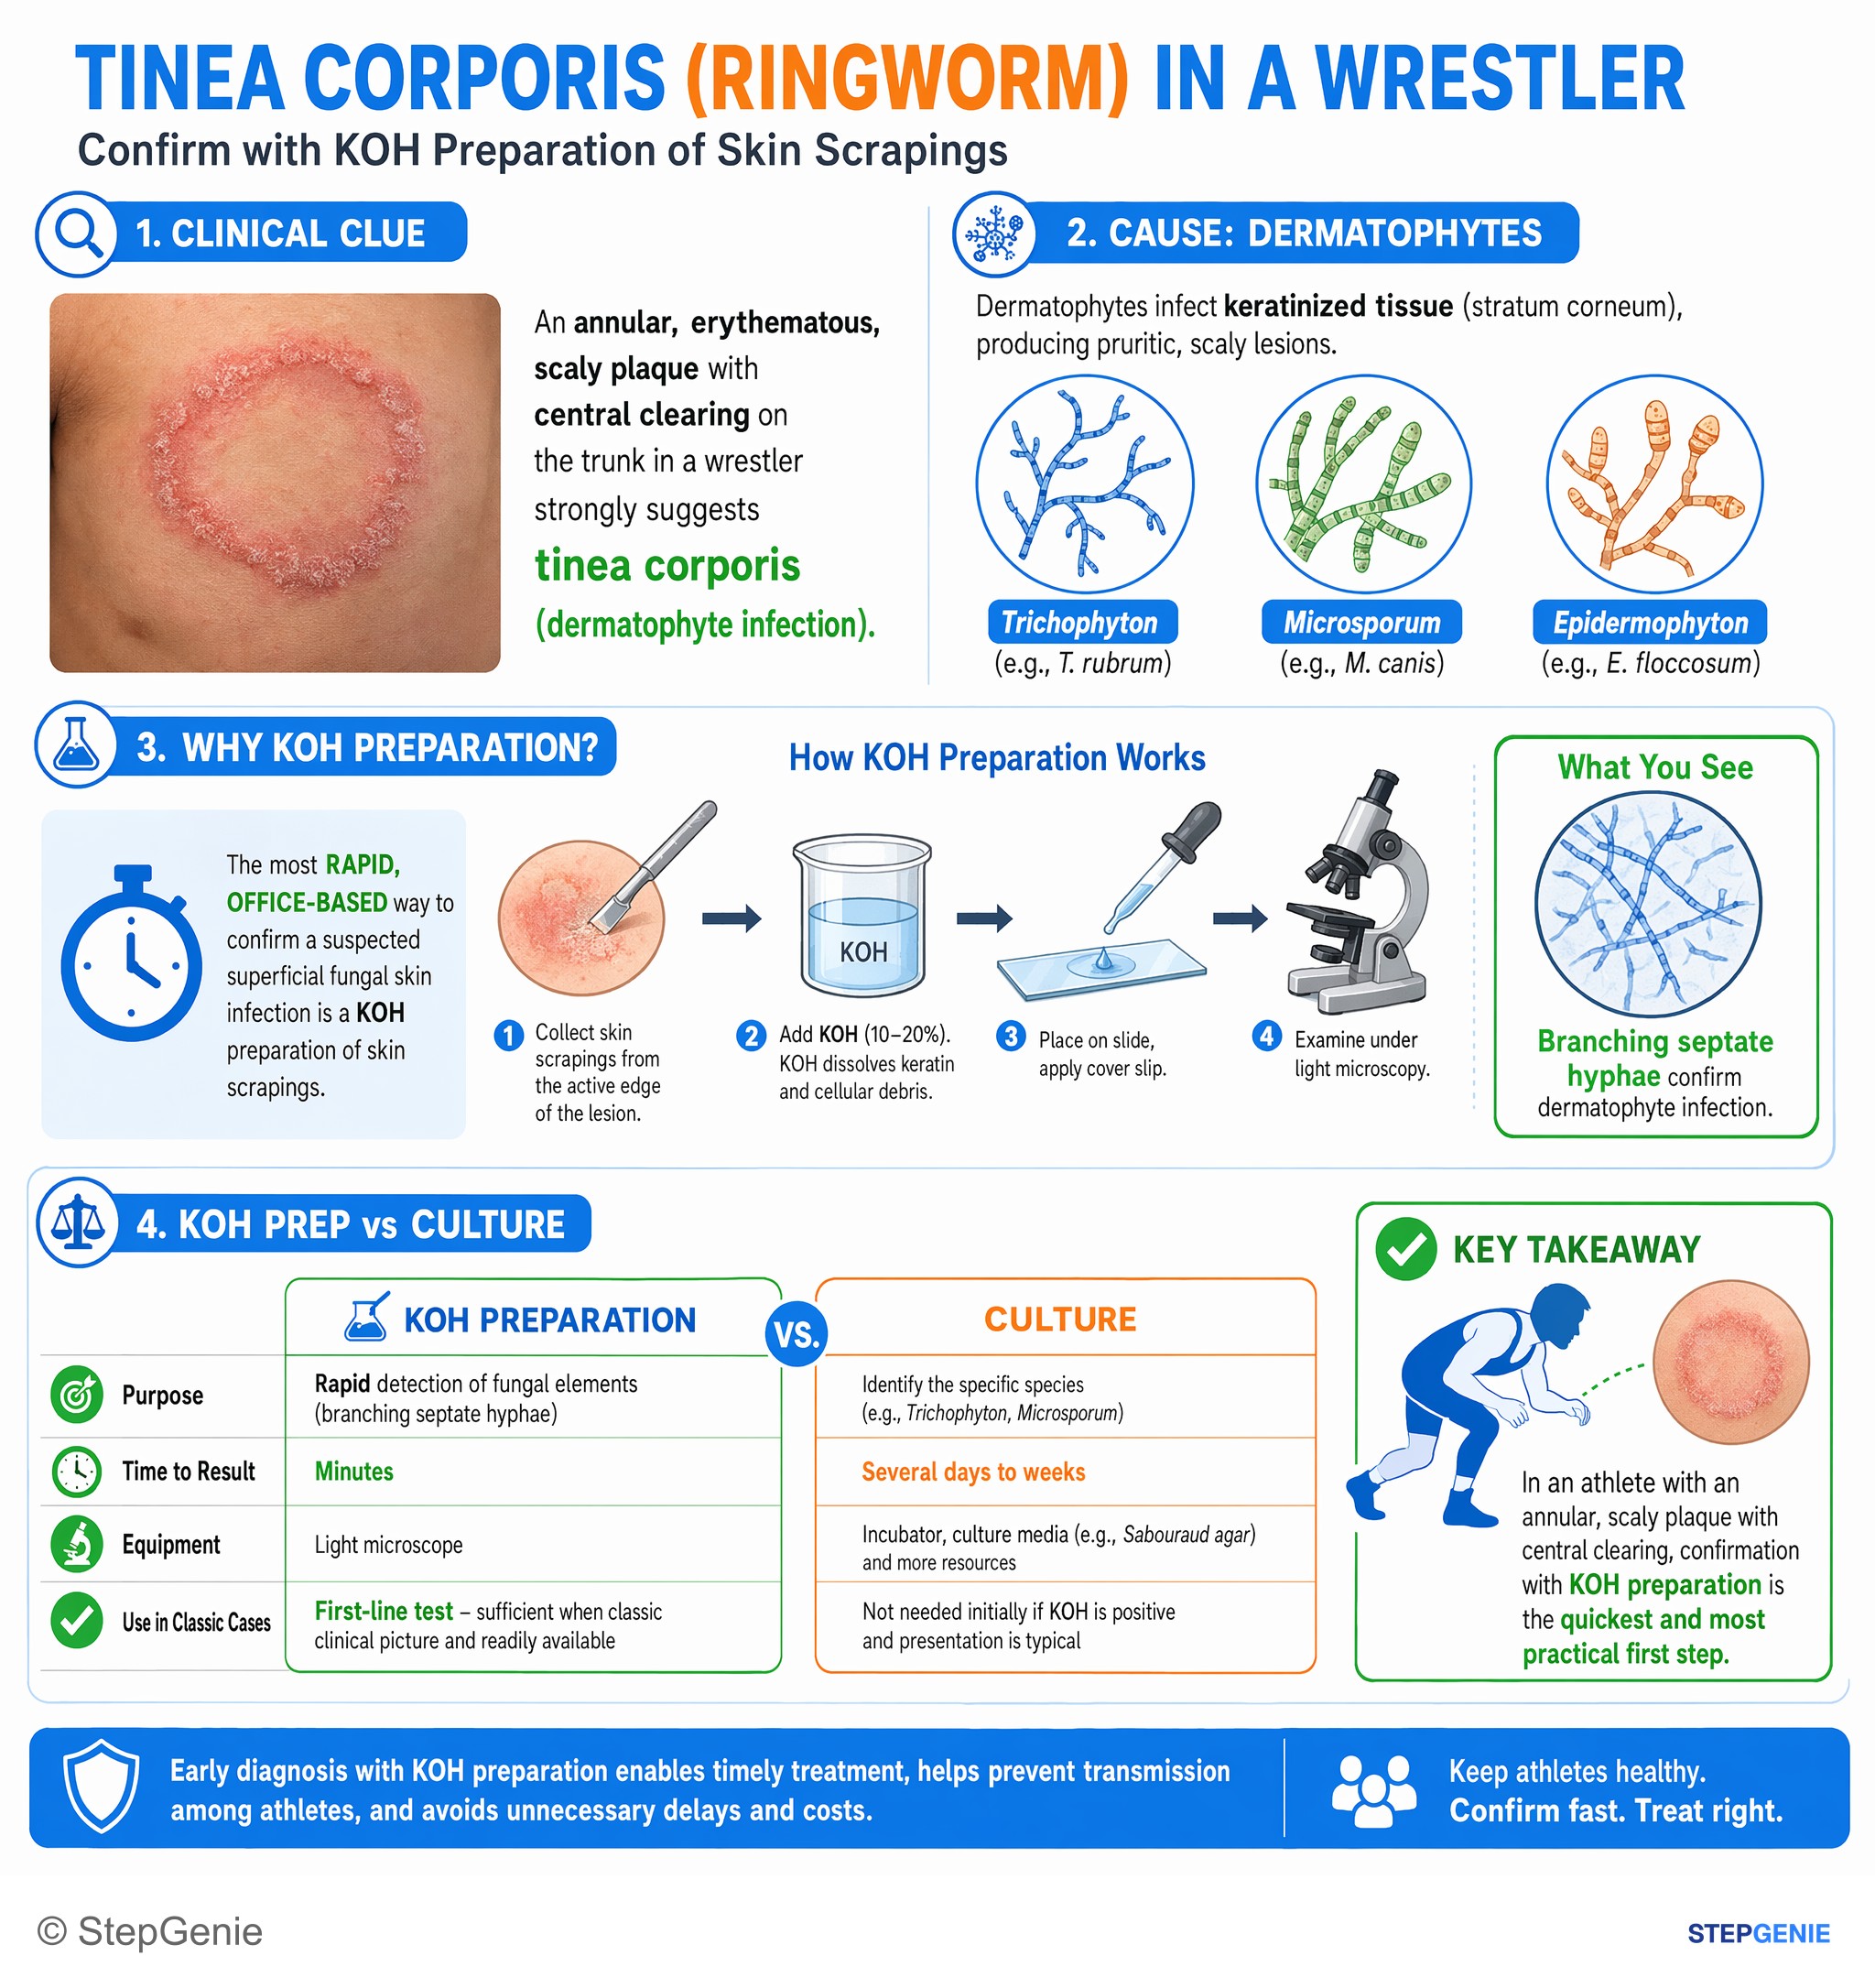
Tinea corporis (ringworm) in an athlete: annular, scaly plaque with central clearing → confirm superficial dermatophyte infection with KOH…
USMLE Step 2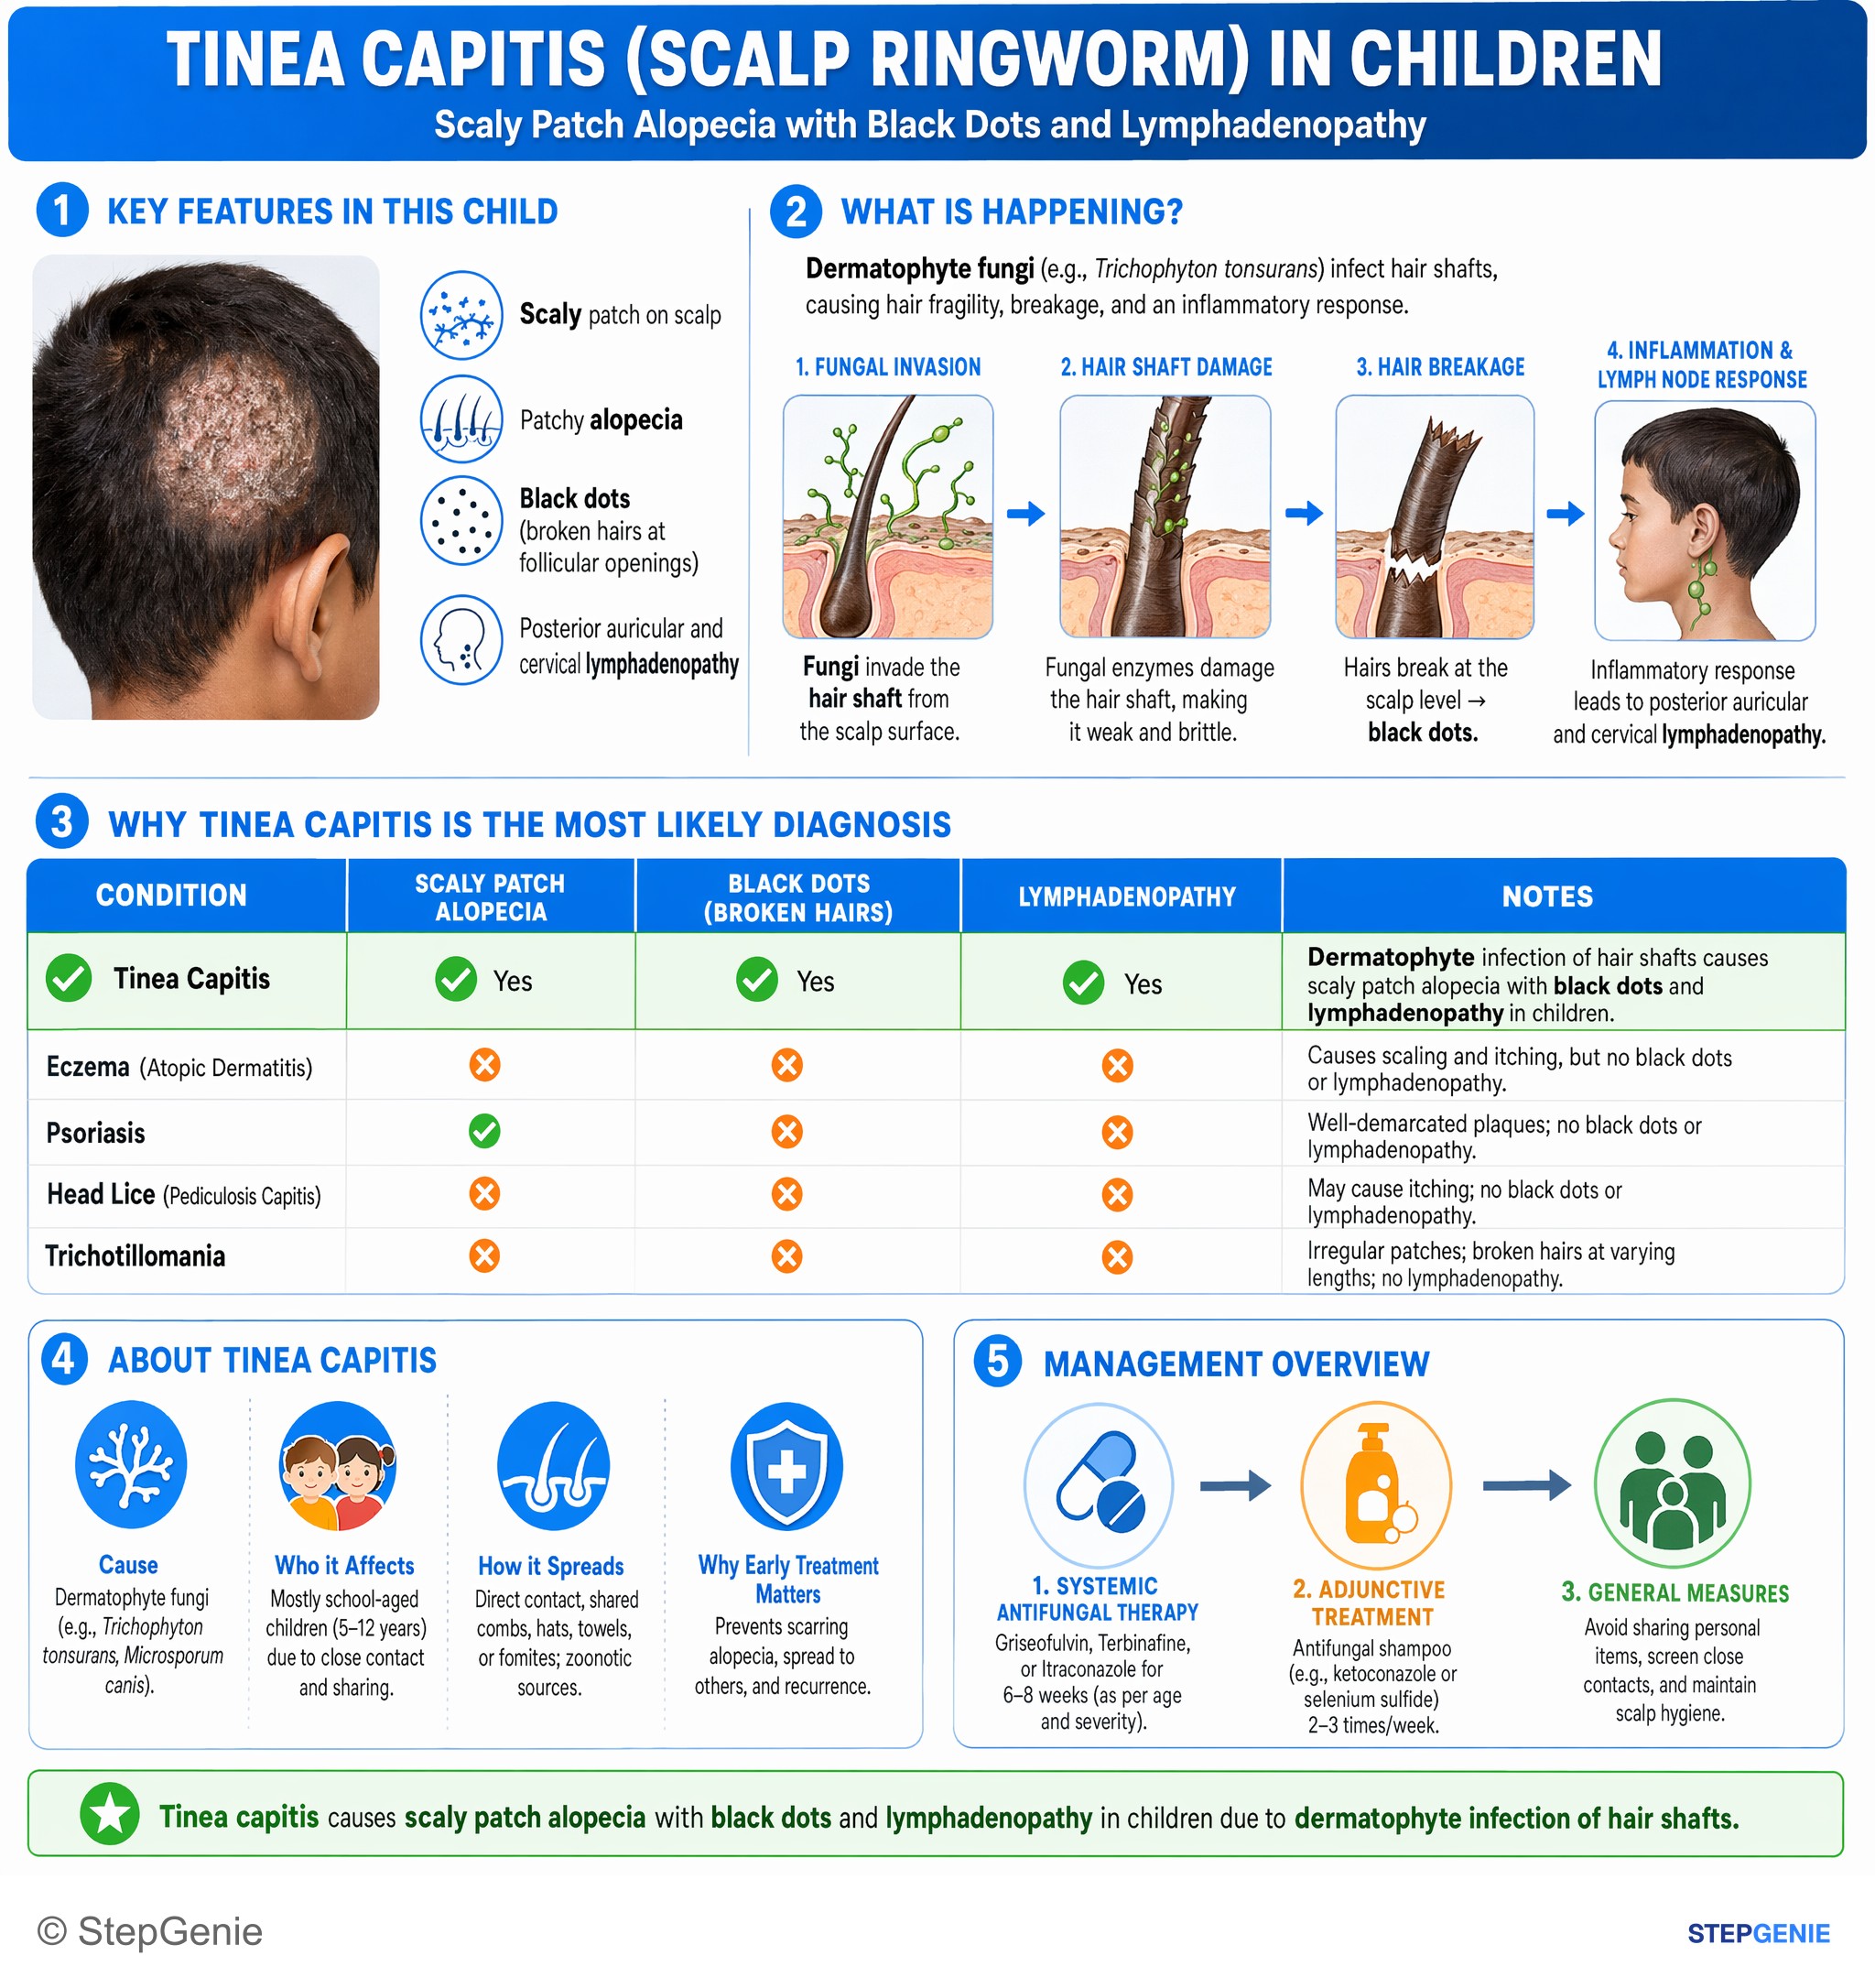
Tinea capitis causes scaly patch alopecia with black dots and lymphadenopathy in children; due to dermatophyte infection of hair shafts.
USMLE Step 2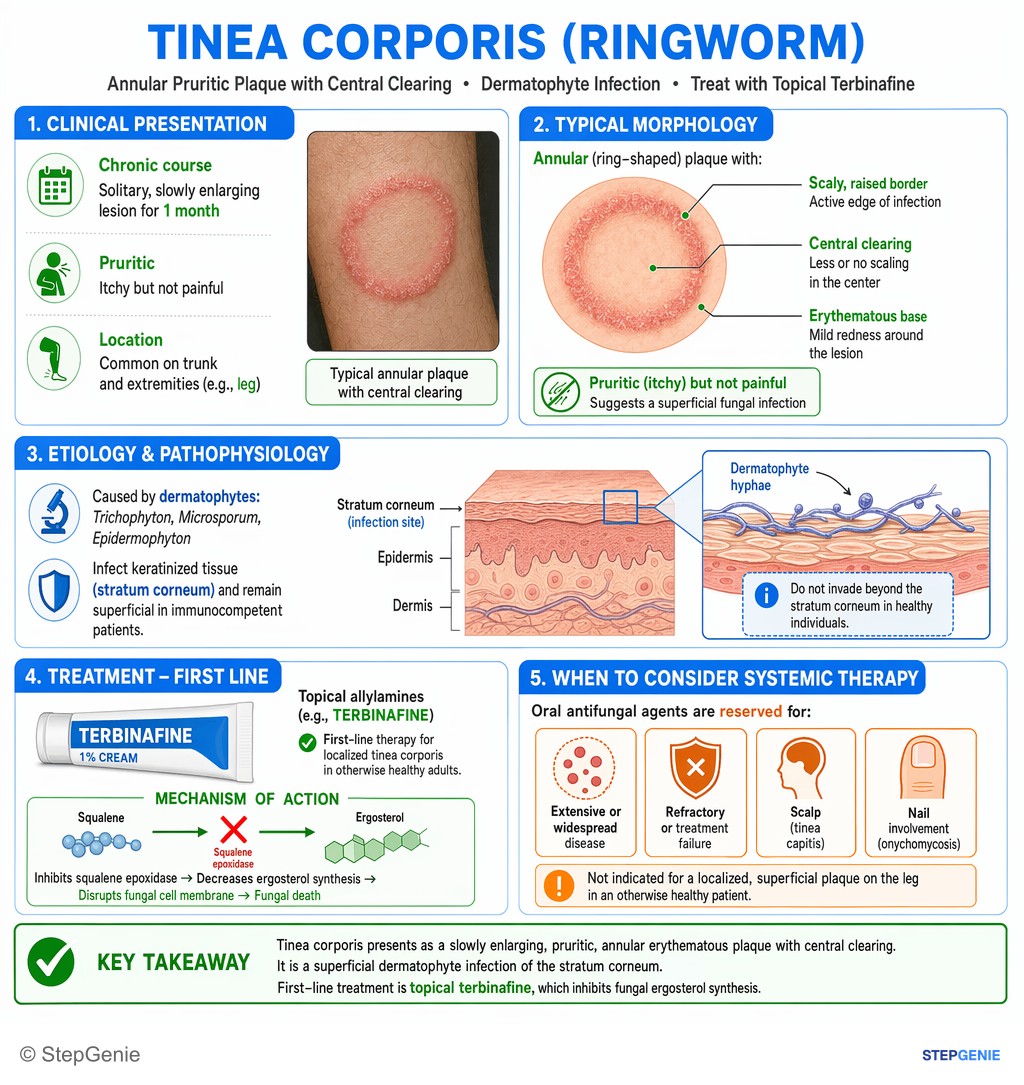
Tinea corporis (annular pruritic plaque with central clearing) is a dermatophyte infection treated with topical terbinafine.
USMLE Step 2Frequently Asked Questions
What are the three dermatophyte genera?
The dermatophytes are Microsporum, Epidermophyton and Trichophyton, remembered as M.E.T. eats keratin. All three are molds that need keratin to survive, so they infect the stratum corneum, hair and nails and rarely invade deeper tissue. Trichophyton rubrum is the most common cause of tinea corporis and a frequent cause of nail infection, while Trichophyton tonsurans causes most tinea capitis in the United States.
Which dermatophyte does not infect hair?
Epidermophyton infects skin and nails but essentially never hair, which is why the mini-mnemonic is Epidermophyton = epidermis plus nails. Microsporum is the mirror image, infecting hair and skin but not nails, and Trichophyton can infect all three. Tinea capitis is therefore caused by Trichophyton or Microsporum.
Which dermatophytes fluoresce under a Wood lamp?
Hairs infected with Microsporum canis or Microsporum audouinii fluoresce blue-green under a Wood lamp. Most dermatophytes seen in the United States do not fluoresce, including Trichophyton tonsurans, the most common cause of tinea capitis, which grows inside the hair shaft and causes black dot tinea. A negative Wood lamp examination therefore never rules out tinea.
Why does tinea capitis need oral treatment?
The infection involves the hair shaft and follicle, and topical antifungals alone are not sufficient to cure it. Oral terbinafine is first line for Trichophyton infections, and oral griseofulvin is preferred for Microsporum in children. Selenium sulfide 2.5% shampoo is added at least twice a week to reduce spread, and children may attend school during treatment.
How do terbinafine and griseofulvin work?
Terbinafine inhibits squalene epoxidase, so toxic squalene accumulates and ergosterol is not made; it is fungicidal, needs baseline liver tests and inhibits CYP2D6. Griseofulvin inhibits microtubule assembly, disrupting the mitotic spindle, and binds newly formed keratin. It is taken with a high-fat meal, is contraindicated in pregnancy, porphyria and liver failure, and induces cytochrome P450, which lowers warfarin's effect.