Respiratory syncytial virus (RSV) is one of those “simple” Step 1 bugs that keeps showing up—because it’s extremely testable. It’s the classic cause of bronchiolitis in infants, it has a distinctive diagnostic clue (syncytia), and it forces you to think through airway obstruction physiology (wheezing + hyperinflation) in a way that connects micro, path, peds, and pharm.
Quick ID: What RSV Is (and Why You Care)
RSV is an enveloped, negative-sense, single-stranded RNA virus in the Paramyxoviridae family (same broader family vibe as parainfluenza and measles).
High-yield identifiers
- Enveloped → relatively fragile in the environment; spread mainly via respiratory droplets and direct contact (fomites are still important in daycare/hospital settings).
- (-)ssRNA → must carry an RNA-dependent RNA polymerase in the virion.
- Causes bronchiolitis and pneumonia in infants/young children
- Famous for syncytia formation via F (fusion) protein
First Aid cross-reference: Microbiology → Viruses → Respiratory viruses (RSV); Pediatrics → Bronchiolitis; Immunology/Pharm sections for palivizumab.
Virology Deep Dive (Step-Relevant)
Structure & Key Proteins
RSV has two “Step 1 favorite” surface proteins:
| Protein | Function | Board-style consequence |
|---|---|---|
| F (fusion) protein | Fuses viral envelope with host cell membrane; also fuses infected cells together | Syncytia (multinucleated giant cells), enhanced cell-to-cell spread |
| G (attachment) protein | Mediates attachment to respiratory epithelium | Tropism for airway epithelium |
Buzzword: Syncytia = multinucleated giant cells formed by fused infected cells (a cytopathic effect).
Mechanism: F protein promotes membrane fusion → infected cells merge.
Pathophysiology: Why RSV Causes Wheeze + Increased Work of Breathing
RSV infects ciliated respiratory epithelial cells, especially in the small airways (bronchioles).
Key downstream effects:
- Inflammation + edema of bronchiolar walls
- Increased mucus production
- Sloughing of necrotic epithelium → debris plugs
- Air trapping (ball-valve effect) → hyperinflation
- Patchy atelectasis can occur from obstruction
How this shows up clinically (connect the dots)
- Wheezing: narrowed bronchioles + mucus plugging
- Crackles: small airway + alveolar involvement, secretions
- Hypoxemia: V/Q mismatch from obstructed/atelectatic regions
- Increased work of breathing: nasal flaring, retractions, tachypnea
First Aid cross-reference: Pathology/Physiology of obstructive disease patterns; Pediatrics bronchiolitis.
Epidemiology & Risk Factors (What NBME Loves)
Who gets RSV?
- Peak: infants < 2 years, especially 2–6 months
- Seasonality: winter (often tested alongside influenza season, but RSV is a pediatric staple)
Risk factors for severe disease
- Prematurity (immature lungs + fewer maternal antibodies)
- Bronchopulmonary dysplasia
- Congenital heart disease
- Immunodeficiency
- Young age (small airway caliber → big effect from mild swelling)
Classic test stem setting: daycare exposure + winter + infant with wheeze.
Clinical Presentation: Bronchiolitis “Picture”
Typical bronchiolitis
Symptoms
- Starts like a URI: rhinorrhea, congestion, low-grade fever
- Progresses to lower respiratory signs: cough, wheezing, tachypnea
Signs
- Intercostal/subcostal retractions
- Nasal flaring
- Diffuse wheezes and/or crackles
- Poor feeding, dehydration in infants
- Apnea can be an early sign in very young infants (especially premature)
Pneumonia (RSV can do both)
- More prominent crackles, hypoxemia
- Can overlap with bronchiolitis findings
Diagnosis: Mostly Clinical (But Know the Tools)
In real life and on Step 1
- Clinical diagnosis is common for typical bronchiolitis.
- Testing is often used for infection control/cohorting in hospitals.
Common diagnostic tests
- RT-PCR of nasopharyngeal swab (sensitive)
- Rapid antigen tests exist but can be less sensitive depending on setting.
Imaging (board relevance)
- CXR may show:
- Hyperinflation
- Peribronchial cuffing
- Patchy atelectasis
- Not required for straightforward cases; used if severe/atypical.
High-yield pitfall: bronchiolitis is viral—antibiotics don’t help unless there’s concern for bacterial superinfection.
Treatment: Supportive First, Targeted Prevention for High-Risk
Main treatment (most important)
Supportive care
- Hydration
- Oxygen if hypoxemic
- Suctioning of nasal secretions (big impact in infants)
- Ventilatory support if severe (HFNC/CPAP/intubation depending on course)
Bronchodilators and steroids: generally not routinely recommended for classic RSV bronchiolitis (Step 2 nuance). Step 1 takeaway: supportive care is the core.
Antivirals (know but don’t overuse)
- Ribavirin: historically used in severe RSV, especially in high-risk/immunocompromised patients; limited routine use due to variable benefit and toxicity/administration issues.
Prevention (very high yield)
Palivizumab
- Monoclonal antibody against RSV F protein
- Used for prophylaxis in high-risk infants (e.g., prematurity, chronic lung disease of prematurity, significant congenital heart disease)
Testable logic chain:
RSV F protein → syncytia + fusion → palivizumab targets F to prevent infection/severe disease.
First Aid cross-reference: Pharm/immunology: monoclonal antibodies; Micro RSV section often mentions palivizumab.
High-Yield Associations & Classic USMLE Clues
Rapid-fire HY facts
- RSV = Paramyxovirus, enveloped, (-)ssRNA
- F protein → syncytia
- Most common cause of bronchiolitis in infants
- Wheezing + hyperinflation pattern
- Treatment: supportive
- Prevention for high risk: palivizumab (anti-F)
Common stem patterns (translate symptoms → diagnosis)
- Infant + winter + URI prodrome → wheeze/retractions → RSV bronchiolitis
- Premature infant with apnea episodes + mild URI signs → consider RSV early
- Question mentions multinucleated giant cells in respiratory epithelium → think RSV (via F protein)
Differential to keep straight
| Condition | Typical age | Hallmark | Common confusion point |
|---|---|---|---|
| RSV bronchiolitis | <2 years | Wheeze, retractions, hyperinflation | Often first wheezing episode |
| Croup (parainfluenza) | 6 mo–3 yr | Barking cough, inspiratory stridor | Upper airway (laryngotracheal) |
| Influenza | any | Abrupt fever, myalgias | Systemic symptoms prominent |
| Asthma | older kids/teens | Recurrent episodic wheeze | Not usually first-time infant bronchiolitis picture |
Mini “First Aid-Style” Memory Hooks (Without the Fluff)
- RSV = Retract (retractions in infants)
- Syncytia = Stuck-together cells (F protein fusion)
- Viral bronchiolitis = Ventilatory support + hydration (supportive care)
Step-Style Questions: What They’re Really Testing
-
Mechanism question: “Which viral protein causes multinucleated giant cells?”
→ F (fusion) protein -
Management question: “Best next step in an infant with RSV bronchiolitis and mild hypoxemia?”
→ Supportive care + oxygen as needed -
Prevention question: “Premature infant entering RSV season—what prophylaxis?”
→ Palivizumab -
Pathophys question: “Why hyperinflation?”
→ Small airway obstruction from edema/mucus/debris → air trapping
Takeaway Summary (What to Have Memorized)
- RSV is an enveloped (-)ssRNA paramyxovirus causing bronchiolitis in infants.
- F protein is the star: fusion + syncytia.
- Clinical picture: URI → wheeze, tachypnea, retractions, hyperinflation.
- Diagnosis is usually clinical; PCR can confirm.
- Treatment is supportive; severe cases may need respiratory support.
- Palivizumab (anti-F) prevents severe RSV in high-risk infants.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
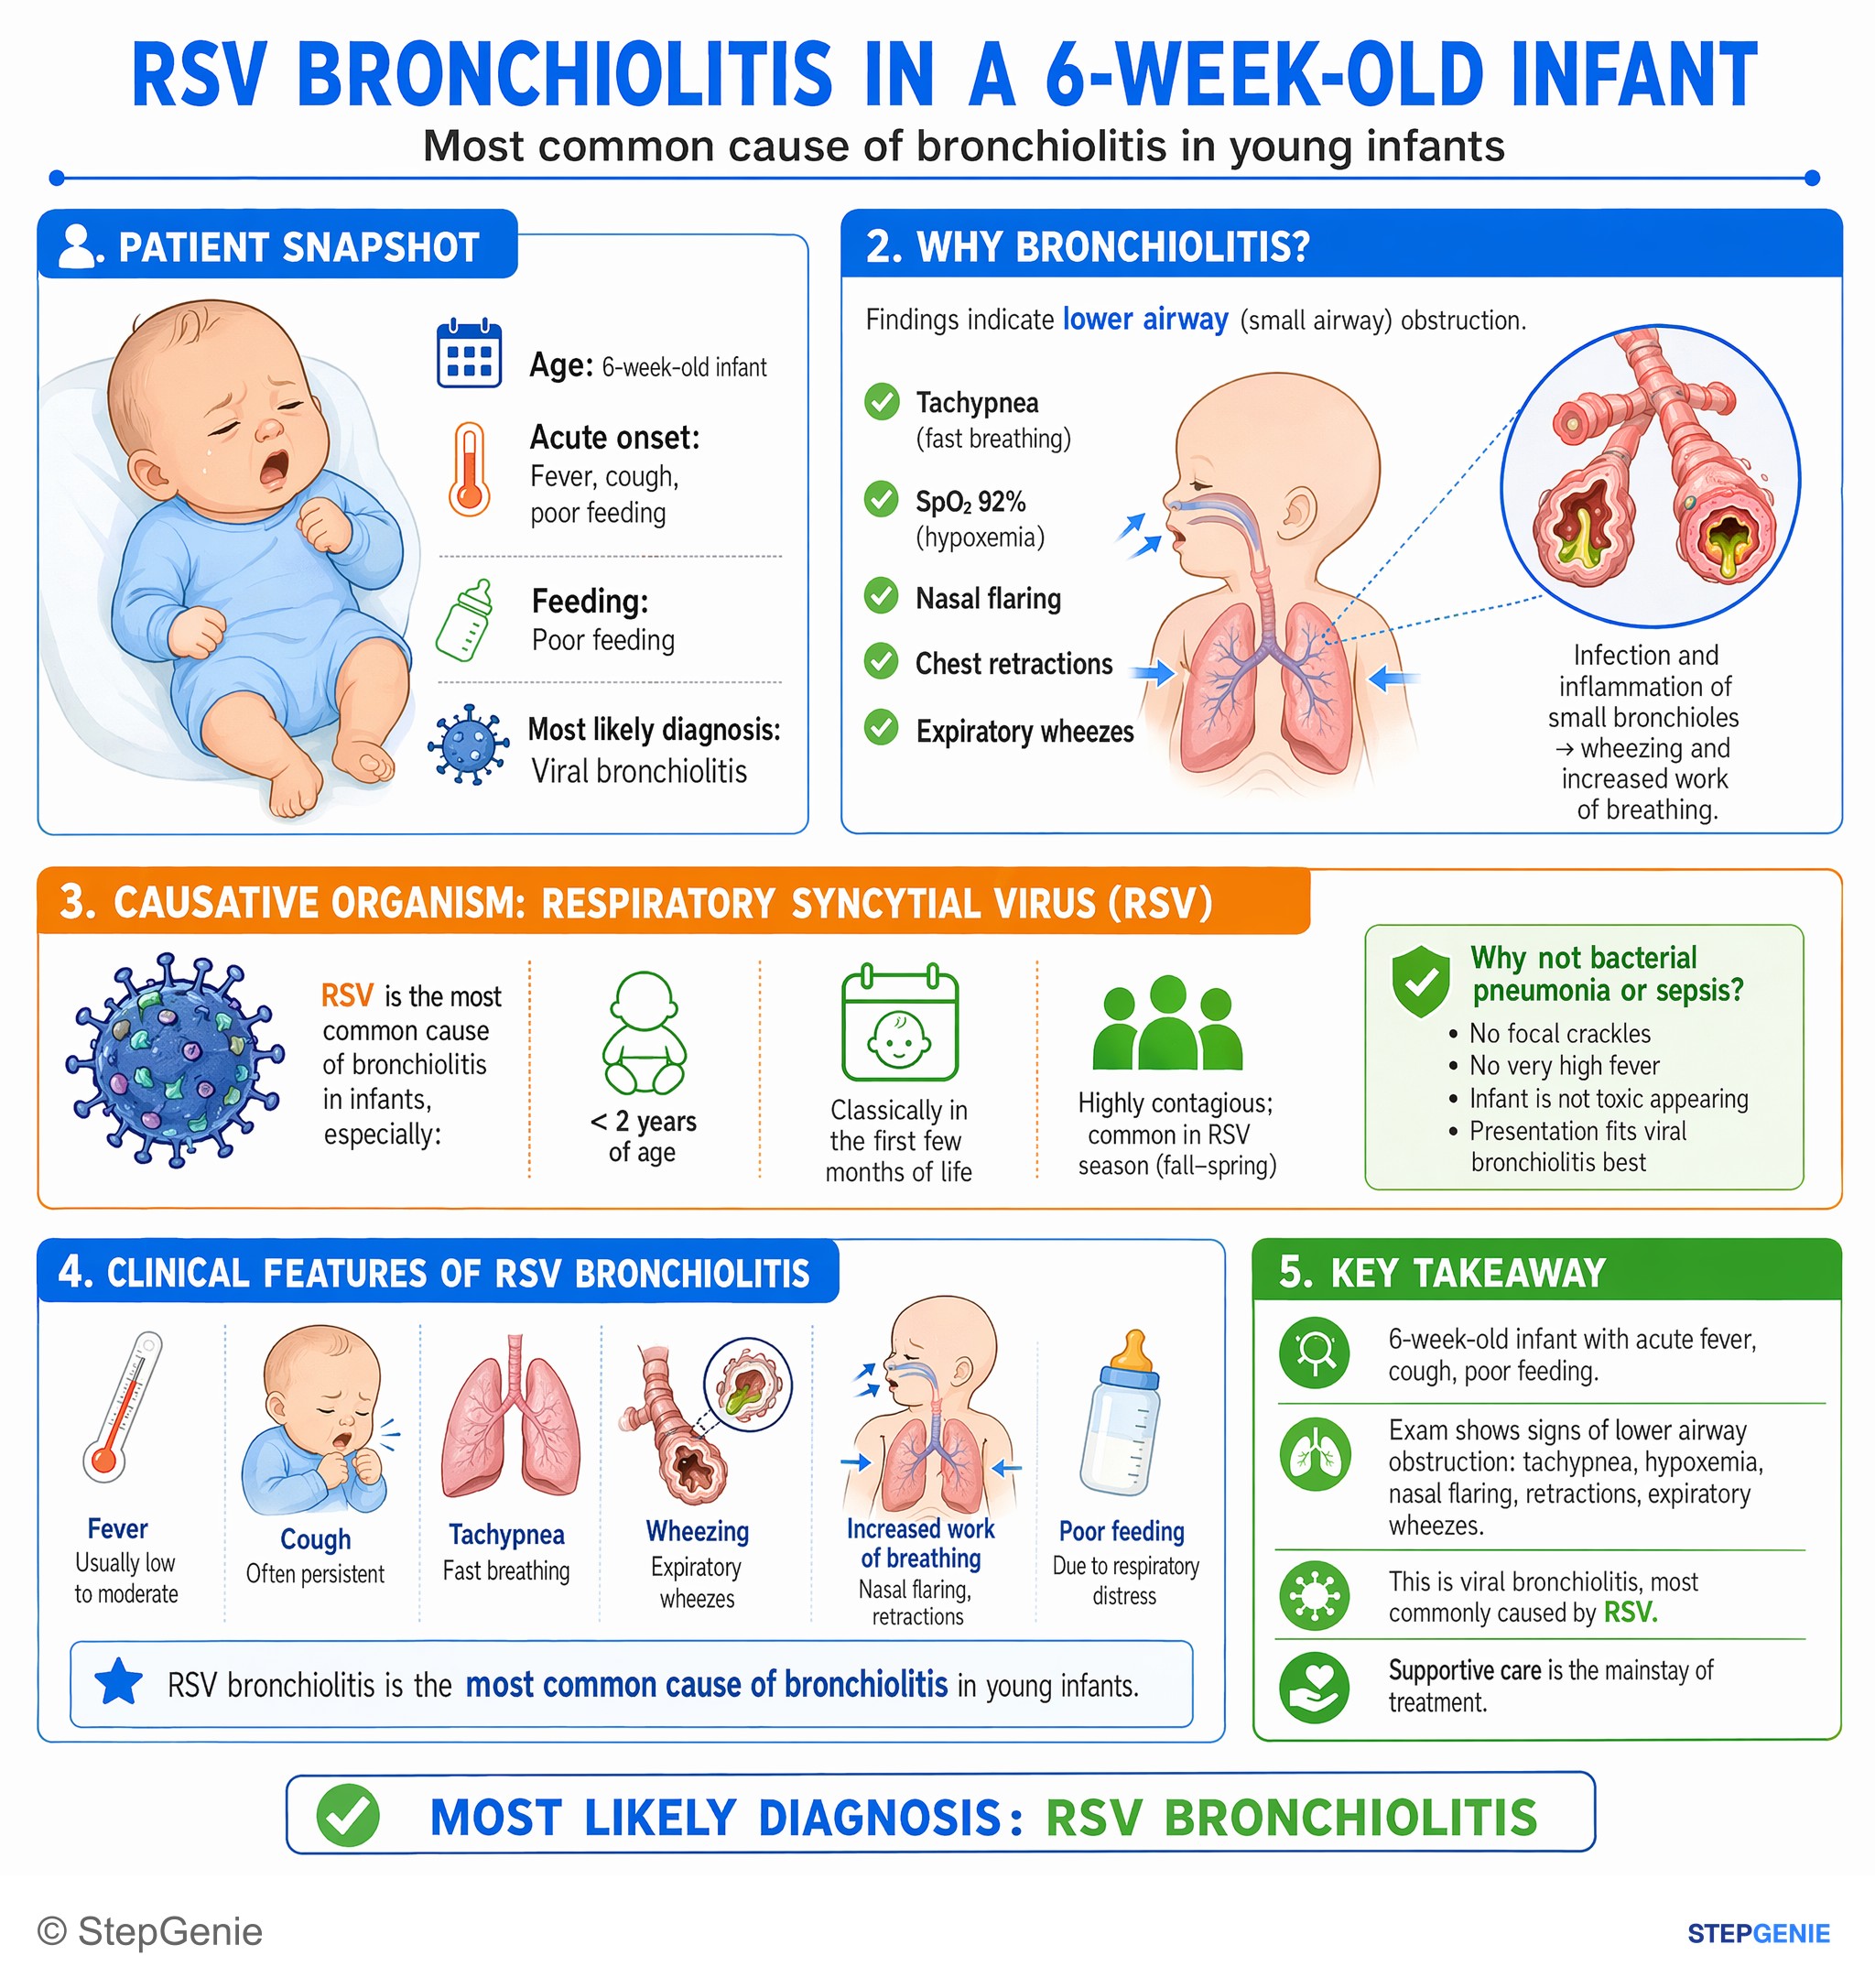
RSV bronchiolitis in young infants causes fever, cough, tachypnea, wheezing, and increased work of breathing; it is the most common cause…
USMLE Step 1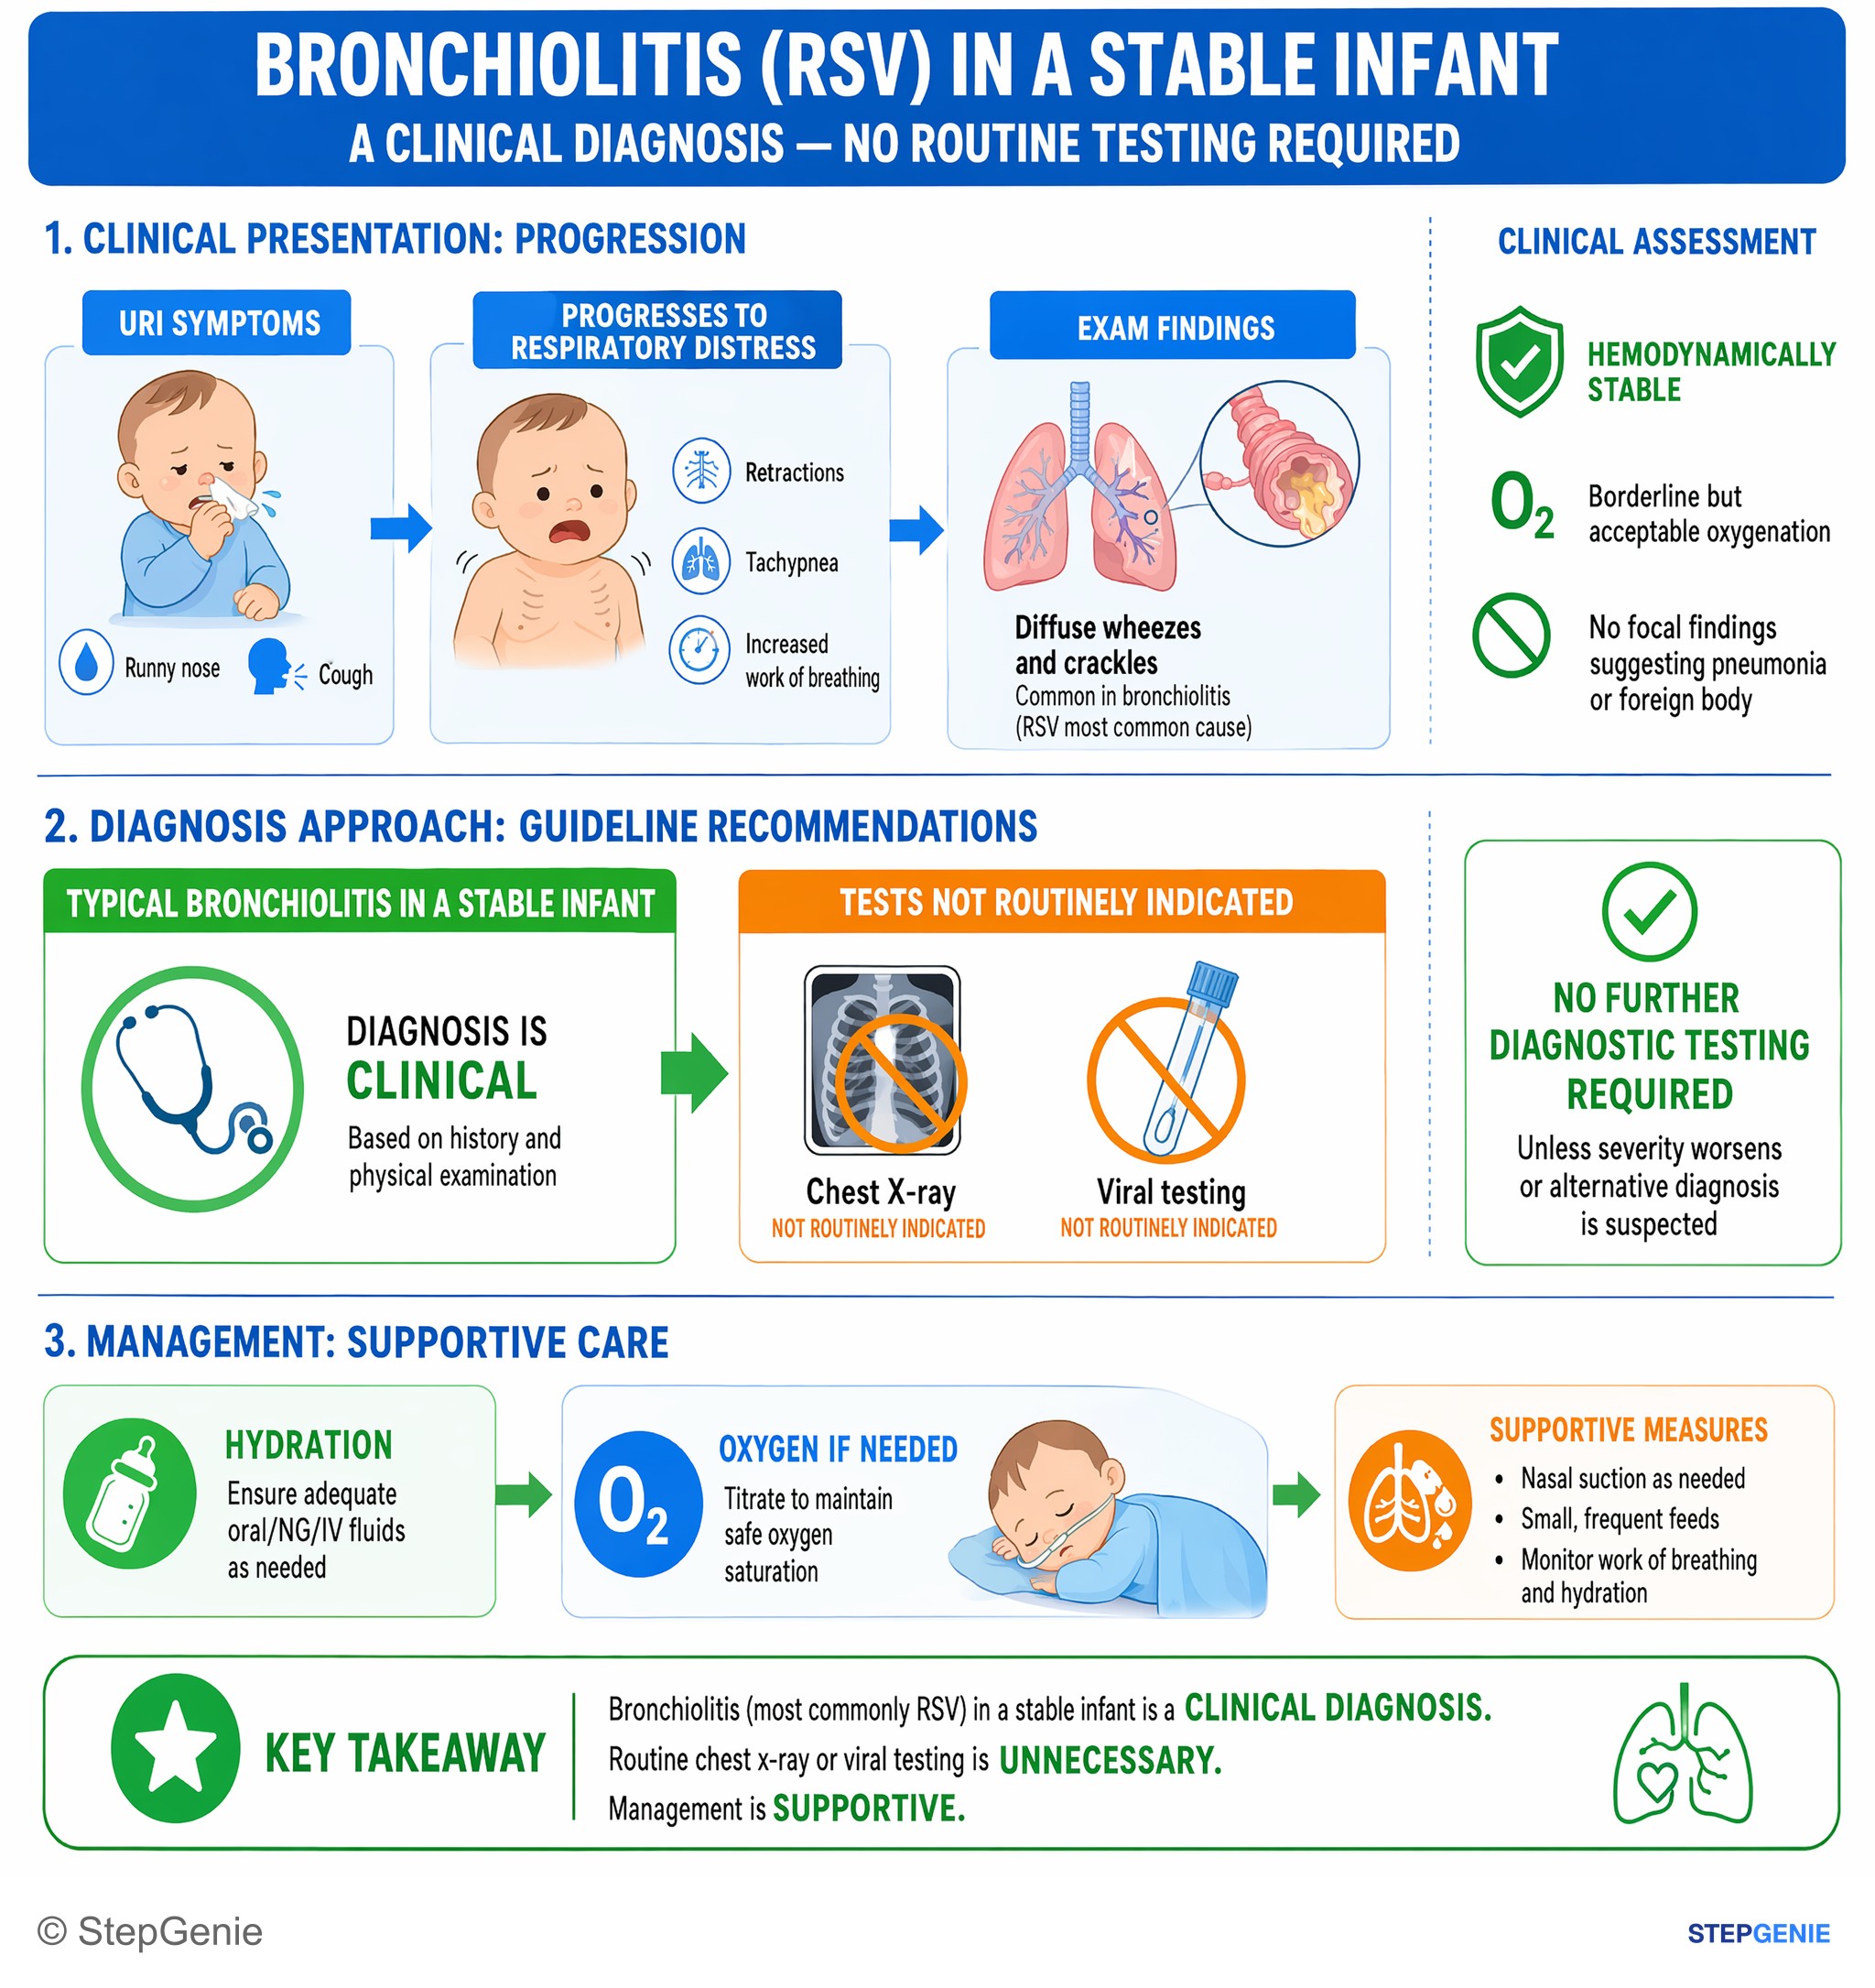
Bronchiolitis (RSV) in a stable infant is a clinical diagnosis; routine imaging or viral testing is unnecessary unless severity or…
USMLE Step 2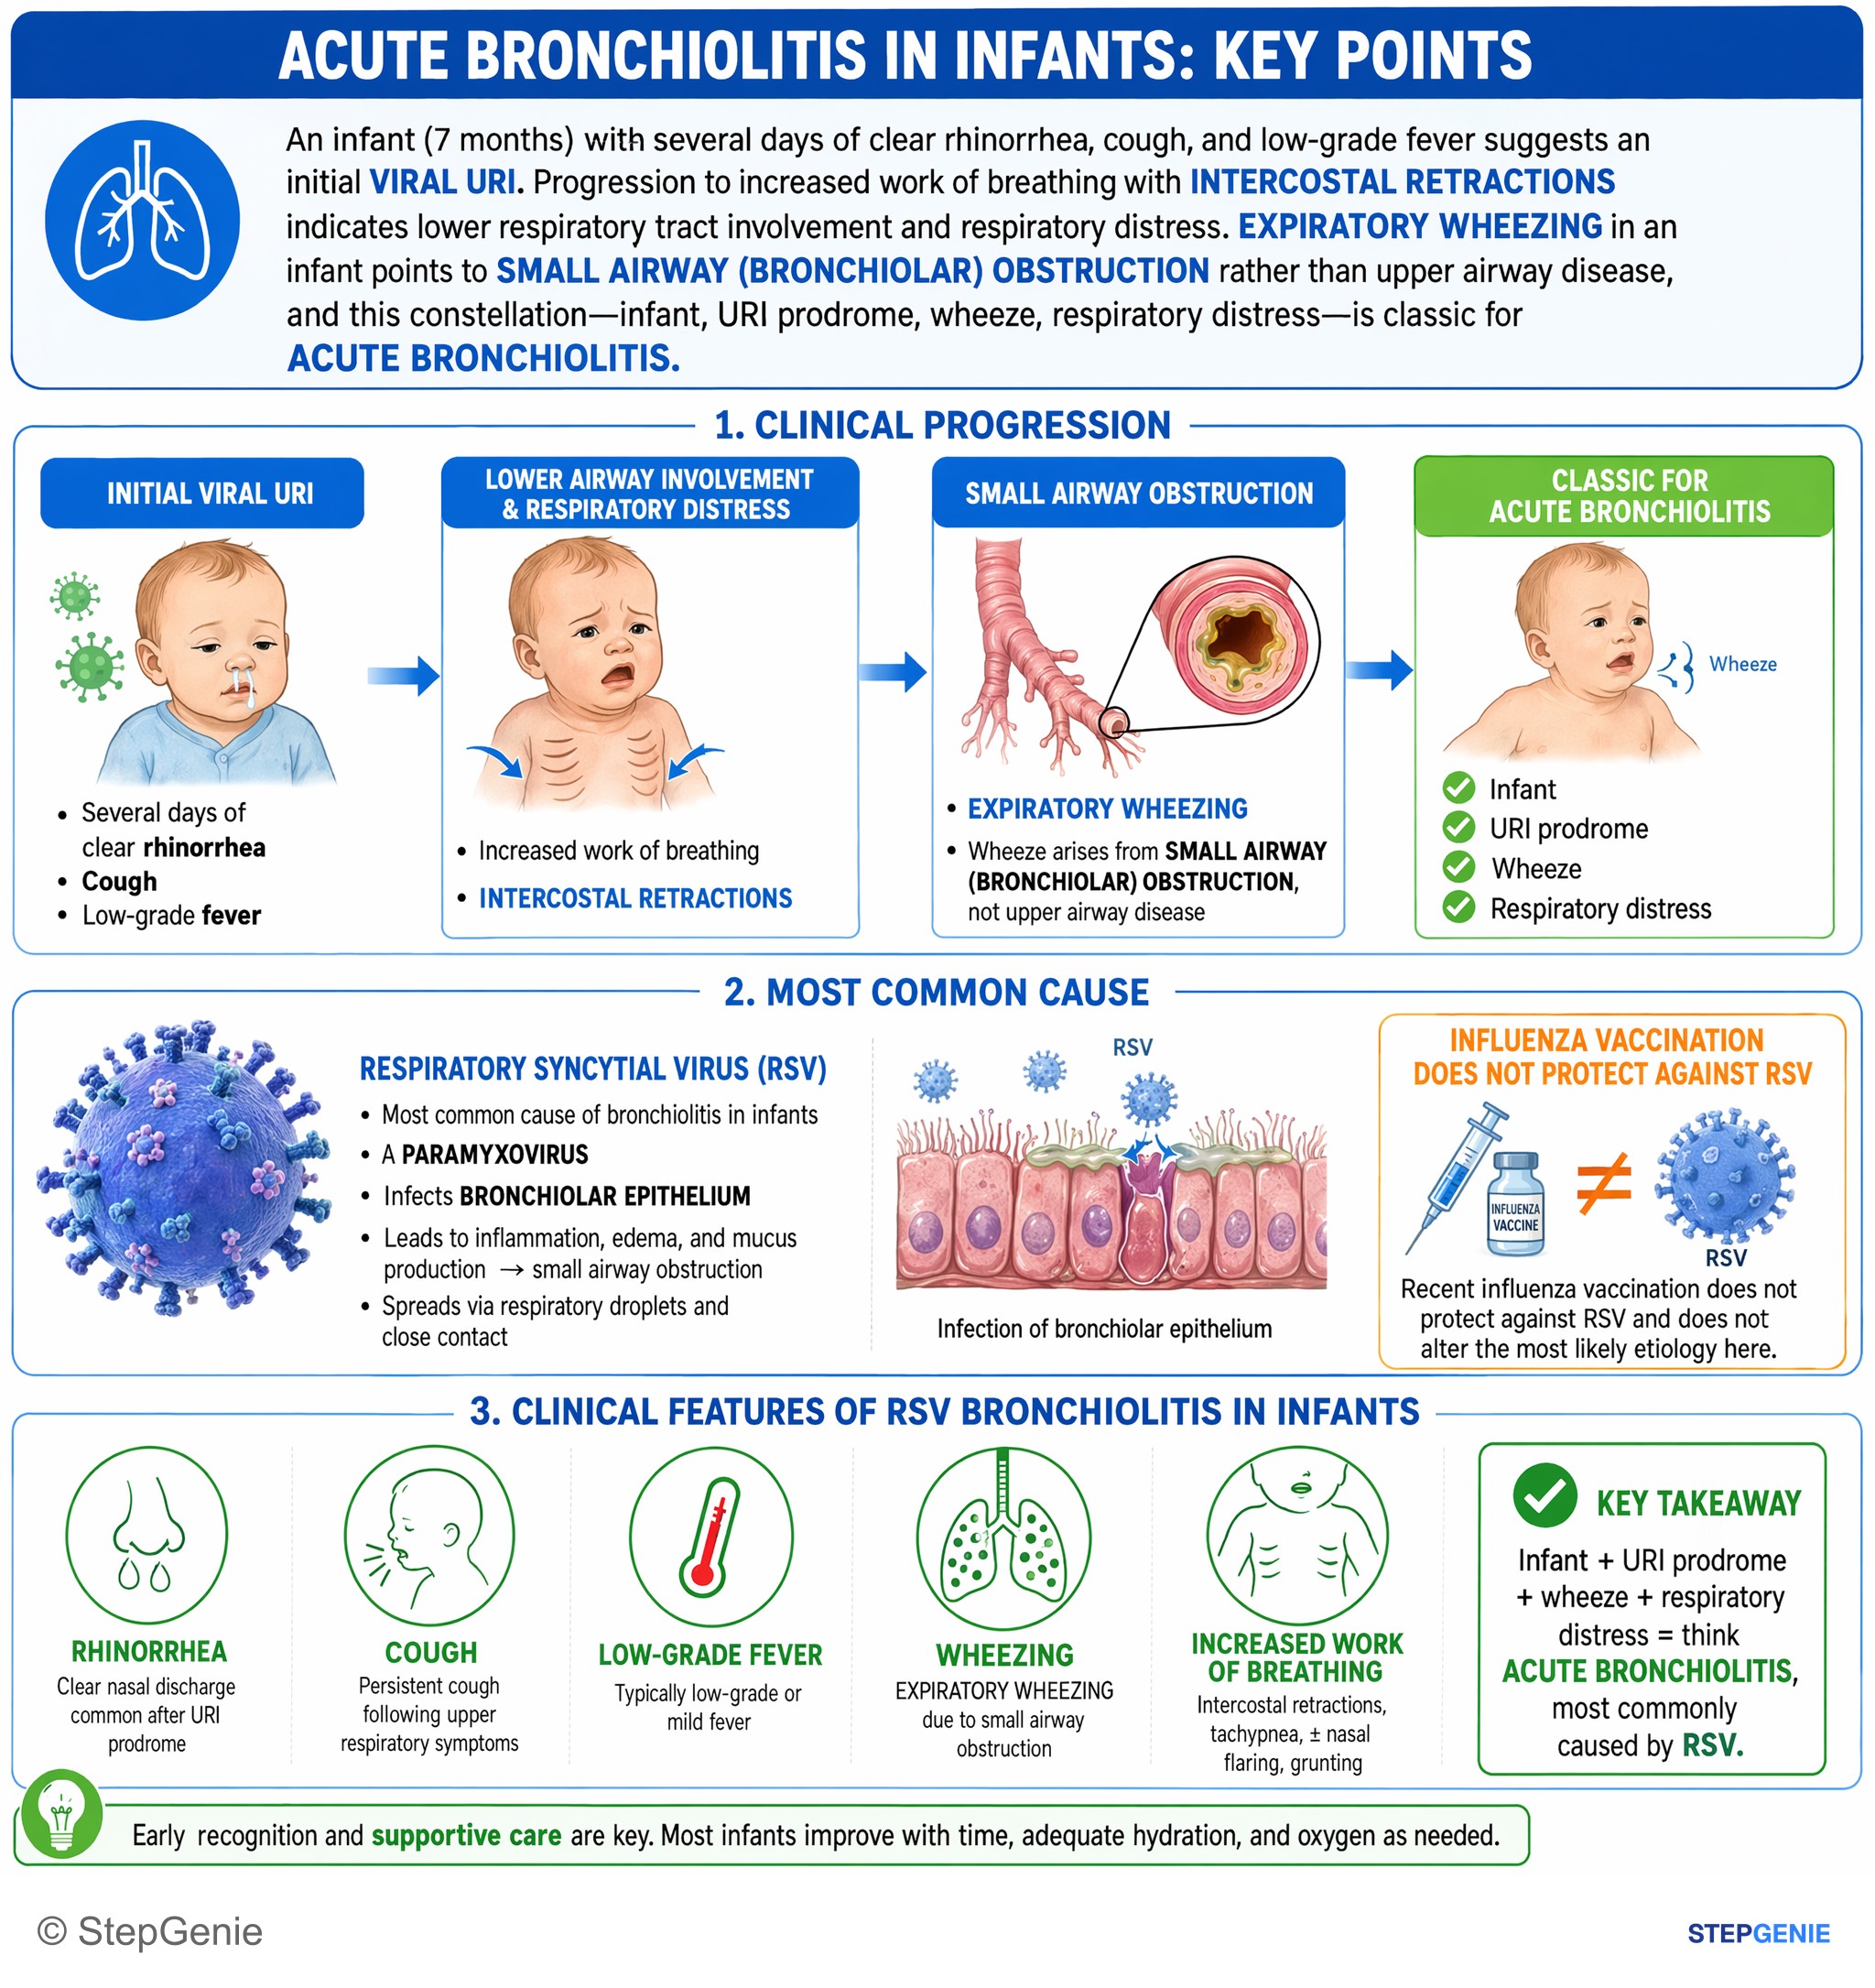
RSV bronchiolitis in infants causes rhinorrhea, cough, low-grade fever, wheezing, and increased work of breathing following an upper…
USMLE Step 1Frequently Asked Questions
Why does RSV cause wheezing and hyperinflation in infants?
RSV causes wheezing and hyperinflation by obstructing the small airways. It infects ciliated respiratory epithelial cells in the bronchioles, leading to inflammation, edema, increased mucus, and sloughing of necrotic epithelium that forms debris plugs. This creates air trapping through a ball-valve effect, which produces hyperinflation and increases the work of breathing.
What causes syncytia in RSV infection?
Syncytia in RSV are caused by the viral F, or fusion, protein. This protein fuses the viral envelope with the host cell membrane and also causes infected respiratory epithelial cells to fuse with each other. The result is multinucleated giant cells, a classic cytopathic effect and one of the most distinctive high-yield clues for RSV.
How is RSV bronchiolitis diagnosed on exams and in real life?
RSV bronchiolitis is usually diagnosed clinically in a typical infant presentation. Common clues include a winter illness in an infant with URI symptoms that progress to cough, wheezing, tachypnea, retractions, and nasal flaring. If testing is needed, RT-PCR from a nasopharyngeal swab is sensitive, while chest x-ray may show hyperinflation, peribronchial cuffing, or patchy atelectasis in severe or atypical cases.
What is the first-line treatment for RSV bronchiolitis?
The first-line treatment for RSV bronchiolitis is supportive care. Management centers on hydration, oxygen if the infant is hypoxemic, and suctioning of nasal secretions, with ventilatory support if severe. Antibiotics do not help because bronchiolitis is viral unless there is concern for bacterial superinfection, and bronchodilators or steroids are generally not routinely recommended for classic RSV bronchiolitis.
Who should get palivizumab for RSV prevention?
Palivizumab is used as prophylaxis for high-risk infants rather than routine treatment of active infection. Classic high-risk groups include infants with prematurity, chronic lung disease of prematurity, or significant congenital heart disease. It targets the RSV F protein, which is also responsible for fusion and syncytia formation, making palivizumab a key prevention clue for RSV.