Rotavirus and norovirus are the classic Step 1/Step 2 “watery diarrhea” viruses—but the exam writers love testing how they’re different: age, settings (daycare vs cruise ship), mechanisms (villous blunting vs transient malabsorption), and what you do about it (rehydration ± vaccine prevention). If you can quickly classify a vomiting/diarrhea stem and tie it to the right virus, you’ll pick up easy points across micro, GI path, and pediatrics.
Big Picture: Where They Fit in Viral Gastroenteritis
Both rotavirus and norovirus cause:
- Acute gastroenteritis
- Watery (non-bloody) diarrhea
- Vomiting
- Fever (often low-grade)
- Dehydration risk (especially infants)
Key differentiator for USMLE stems:
- Rotavirus → kids, severe dehydration, villous atrophy
- Norovirus → all ages, outbreaks (cruise ships, dorms), very contagious, prominent vomiting
High-Yield Comparison Table (Step-Style)
| Feature | Rotavirus | Norovirus |
|---|---|---|
| Virus family | Reoviridae | Caliciviridae |
| Genome | dsRNA, segmented | +ssRNA |
| Envelope? | Non-enveloped | Non-enveloped |
| Classic population | Infants/young children | All ages |
| Classic setting | Daycare, pediatrics wards | Cruise ships, schools, nursing homes, restaurants |
| Main symptoms | Watery diarrhea, vomiting, fever | Explosive vomiting, watery diarrhea, cramps |
| Pathophysiology buzzword | Villous atrophy → malabsorption | Acute mucosal dysfunction (transient) |
| Diagnosis (real life) | Stool PCR/antigen | Stool PCR (outbreaks), often clinical |
| Treatment | Oral/IV rehydration | Oral/IV rehydration |
| Prevention | Live attenuated oral vaccine | Hygiene + outbreak control (no routine vaccine) |
Rotavirus Deep Dive (Reoviridae)
Definition & Virology (What to Recognize on Step 1)
- Reoviridae, non-enveloped
- Double-stranded RNA (dsRNA), segmented
- Major cause of severe gastroenteritis in infants/young children worldwide
First Aid cross-reference (concepts):
- “Reovirus (rotavirus): dsRNA, segmented, gastroenteritis in children, live attenuated vaccine”
- Viral gastroenteritis page/section (varies by edition under GI viruses)
Pathophysiology (Why the Diarrhea Is Watery)
Rotavirus infects mature enterocytes in the small intestine, leading to:
- Villous blunting/atrophy → decreased absorptive surface area
- Malabsorption → osmotic component to diarrhea
- Secretory component also contributes (Step-level takeaway: villous atrophy → watery diarrhea)
High-yield pathology phrase: “Villous atrophy of small intestine → malabsorption → watery diarrhea.”
Clinical Presentation (Classic Stem)
- Infant/toddler (often 6–24 months)
- Fever + vomiting followed by profuse watery diarrhea
- Can cause severe dehydration (sunken fontanelle, decreased tears/urine, tachycardia)
- Often in winter months in temperate climates (helpful but not always tested)
Step clue: A vaccinated child has lower risk—vaccine history may be mentioned.
Diagnosis (Exam vs Real Life)
- Usually clinical if straightforward
- Confirmatory tests in practice:
- Stool antigen assays or RT-PCR
On USMLE, you’re more likely to diagnose via age + profuse watery diarrhea + dehydration than via lab tests.
Treatment
- Supportive care is the answer
- Oral rehydration therapy (ORT) if mild/moderate
- IV fluids if severe dehydration or inability to tolerate PO
- No routine antivirals
Prevention (Super High-Yield)
- Live attenuated oral vaccine (given in infancy)
- Protects strongly against severe disease and hospitalization
USMLE vaccine association: live vaccine → think about standard live-vaccine rules (e.g., avoid in certain severe immunodeficiency states), but routine pediatric schedules include it.
Norovirus Deep Dive (Caliciviridae)
Definition & Virology
- Caliciviridae, non-enveloped
- Positive-sense single-stranded RNA (+ssRNA)
- Leading cause of acute gastroenteritis outbreaks across all ages
First Aid cross-reference (concepts):
- “Norovirus: cruise ships, acute gastroenteritis, vomiting/diarrhea, highly contagious”
Pathophysiology (How It Produces Symptoms)
Norovirus causes acute inflammation/dysfunction of intestinal mucosa leading to:
- Transient malabsorption
- Disruption of epithelial function
- Net effect: acute watery diarrhea + prominent vomiting
Step-level: you usually won’t need detailed toxin/protein names—focus on outbreaks + contagiousness + rapid onset.
Clinical Presentation (Classic Stem)
- Any age, often adolescents/adults
- Abrupt onset nausea and projectile/explosive vomiting, watery diarrhea, abdominal cramps
- Commonly linked to:
- Cruise ships
- Dorms/daycares
- Nursing homes
- Restaurants/catered events
Transmission high-yield:
- Fecal–oral
- Extremely low infectious dose
- Can spread via contaminated food/water and person-to-person
Diagnosis
- Often clinical (especially in outbreak scenario)
- RT-PCR of stool can confirm during outbreaks
Treatment
- Supportive (ORT/IV fluids as needed)
- Symptomatic management (antiemetics sometimes in practice), but Step answers: rehydration
Prevention & Infection Control (Frequently Tested Conceptually)
Because it’s non-enveloped, norovirus is relatively hardy in the environment and can persist on surfaces.
- Hand hygiene, surface disinfection, isolation/cohorting in outbreaks
- No routine vaccine
How to Nail the USMLE Stem: Rapid Pattern Recognition
If the stem says…
“Infant with severe watery diarrhea, dehydration, daycare” → Rotavirus
“Cruise ship/dorm/nursing home outbreak with vomiting” → Norovirus
Quick discriminator checklist
- Age: young child → rota; any age/outbreak → noro
- Setting: daycare/peds → rota; cruise ship/catered outbreak → noro
- Mechanism: villous atrophy/malabsorption → rota (classic)
- Key symptom emphasis: vomiting is big in both, but explosive vomiting + outbreak screams noro
High-Yield Associations & Classic Exam Traps
1) “Watery vs bloody” diarrhea
- Rota/Noro → watery, typically no fecal leukocytes
- Bloody diarrhea pushes you toward invasive bacteria (Shigella, Campylobacter, EHEC, etc.)
2) Dehydration is the complication they want you to treat
If asked for next best step:
- Assess hydration status
- Start oral rehydration if possible
- IV fluids if severe (lethargy, poor perfusion, hypotension, inability to drink)
3) Vaccine clue (Rotavirus)
If they mention an infant not vaccinated (or countries with low vaccine uptake), rotavirus becomes more likely.
4) Non-enveloped = hardy
Both are non-enveloped, which is often associated with:
- Environmental stability
- Fecal–oral transmission
- Resistance to drying/acid (general principle)
Mini “First Aid-Style” Memory Hooks
- Rota = Reovirus, RNA double-stranded, Really bad diarrhea in Rugrats (kids)
- Noro = Nursing homes / Navy ships (cruise ships), Nausea + Noxious vomiting outbreaks
Practice-Question Style Vignettes (Fast)
- 9-month-old with fever, vomiting, then profuse watery diarrhea; signs of dehydration; daycare exposure → Rotavirus, treat with rehydration, prevent with live oral vaccine.
- Several adults on a cruise ship develop abrupt vomiting and watery diarrhea within 24–48 hours → Norovirus, manage outbreak + supportive care.
Key Takeaways (What You Should Remember on Test Day)
- Rotavirus: Reoviridae, dsRNA segmented, villous atrophy, severe watery diarrhea in infants, live oral vaccine.
- Norovirus: Caliciviridae, +ssRNA, outbreaks (cruise ships/nursing homes), explosive vomiting, supportive care.
- Both: non-enveloped, fecal–oral, watery diarrhea, rehydration is treatment.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
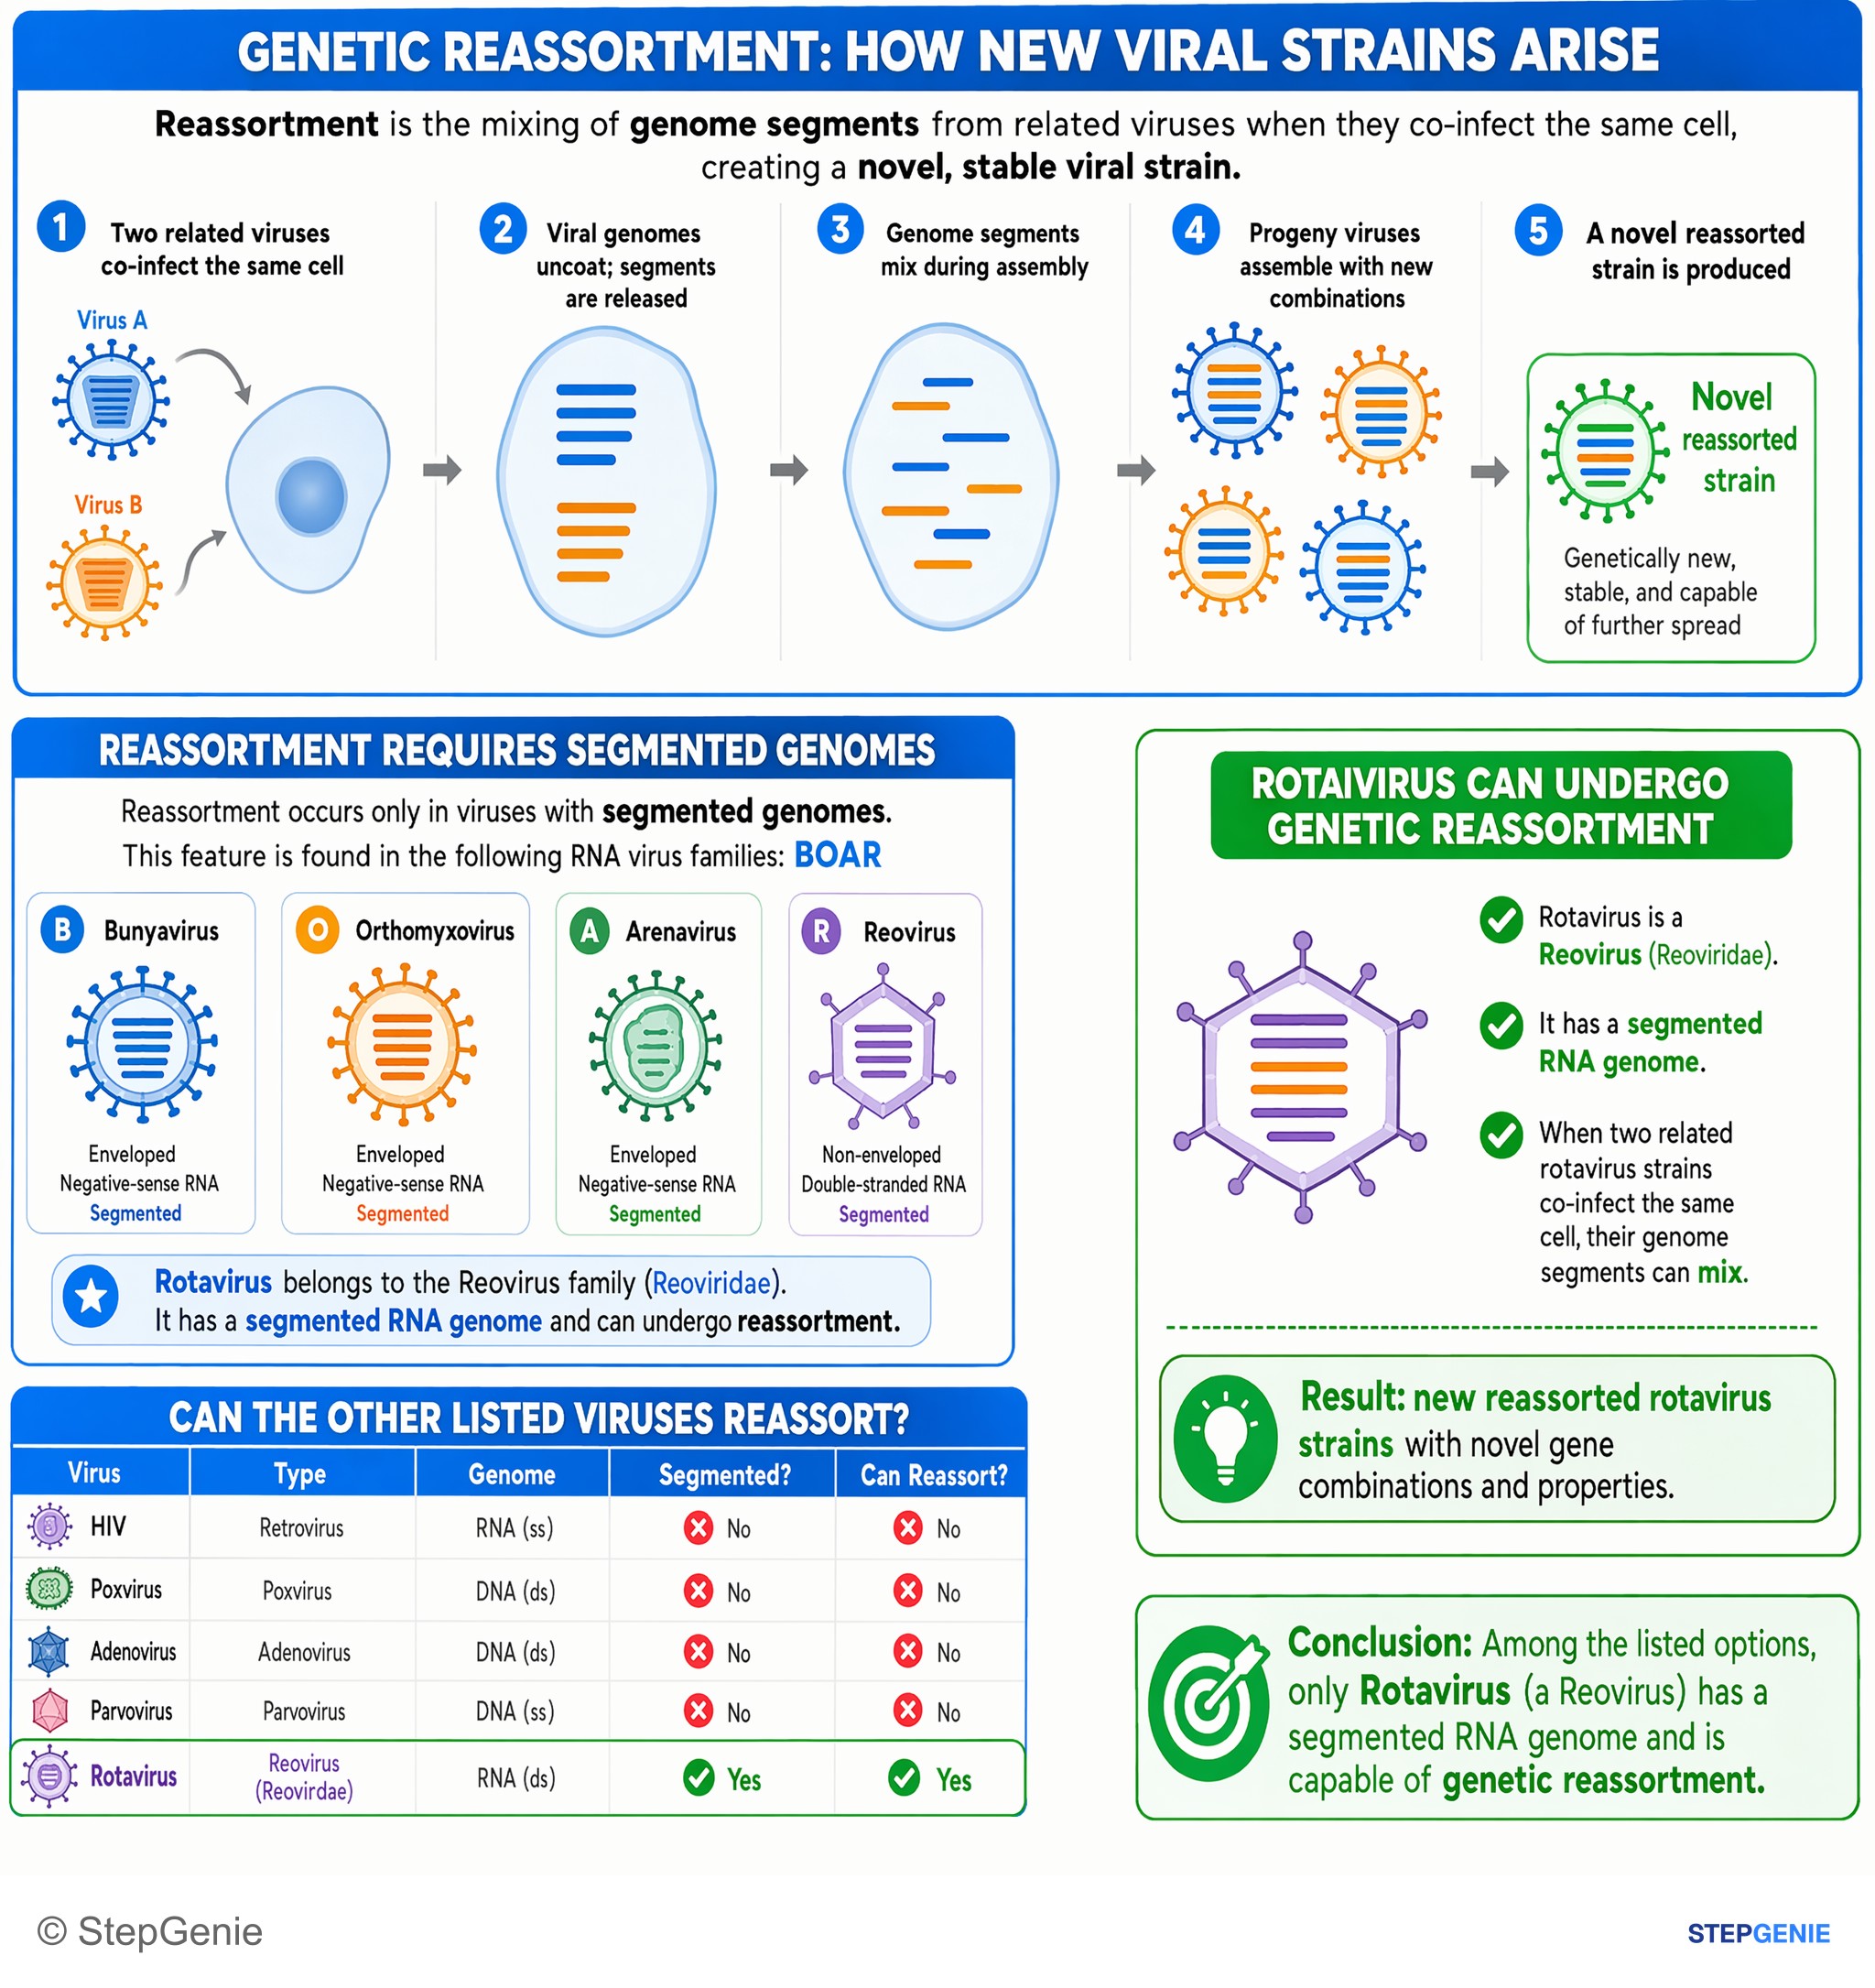
Rotavirus, a segmented RNA virus (Reoviridae), can undergo genetic reassortment when two related strains co-infect the same cell, creating…
USMLE Step 1Frequently Asked Questions
How do you tell rotavirus from norovirus on a USMLE diarrhea stem?
The fastest way is to use age and setting. Rotavirus classically affects infants and young children, often in daycare or pediatric settings, and is associated with profuse watery diarrhea and severe dehydration. Norovirus affects all ages and is famous for outbreaks on cruise ships, in dorms, nursing homes, schools, and restaurants, with very prominent abrupt vomiting plus watery diarrhea.
Why does rotavirus cause watery diarrhea?
Rotavirus causes watery diarrhea by damaging mature enterocytes in the small intestine and producing villous blunting or atrophy. This reduces the absorptive surface area, leading to malabsorption and an osmotic component of diarrhea. A secretory component also contributes, but the key Step-level mechanism is villous atrophy causing malabsorption and therefore watery, non-bloody diarrhea.
Why is norovirus so contagious in outbreaks like cruise ships and dorms?
Norovirus is highly contagious because it spreads by the fecal-oral route, has an extremely low infectious dose, and can be transmitted through contaminated food, water, and person-to-person contact. It is also non-enveloped, which makes it relatively hardy in the environment and able to persist on surfaces. That combination makes rapid spread in shared living or dining settings very likely.
What is the first-line treatment for rotavirus and norovirus?
The first-line treatment for both rotavirus and norovirus is supportive rehydration. Oral rehydration therapy is used for mild to moderate illness, while IV fluids are given when dehydration is severe or the patient cannot tolerate oral intake. There are no routine antivirals emphasized for these infections, so the exam answer is usually rehydration and supportive care.
Is there a vaccine for rotavirus or norovirus?
There is a live attenuated oral vaccine for rotavirus, but there is no routine vaccine for norovirus. Rotavirus vaccination is given in infancy and strongly protects against severe disease and hospitalization. For norovirus, prevention focuses on hand hygiene, surface disinfection, and outbreak control measures such as isolation or cohorting, especially because the virus can persist on surfaces.