A pentose phosphate pathway mnemonic that covers the whole map is "oxidize, then shuffle": the one-way oxidative phase makes 2 NADPH and 1 CO₂ (G6PD is the rate-limiting enzyme), and the two-way non-oxidative phase swaps sugar carbons without making NADPH. Then add "three Ts": transketolase needs thiamine and transfers two carbons.
The pathway, also called the hexose monophosphate (HMP) shunt, runs in the cytosol and branches off glycolysis at glucose-6-phosphate. Boards use it for three diseases: G6PD deficiency (red cells run short of NADPH and hemolyze under oxidant stress), thiamine deficiency (low red-cell transketolase activity, Wernicke encephalopathy) and, through NADPH oxidase, chronic granulomatous disease.
The hooks below are StepGenie's own memory aids, not standard textbook mnemonics; every fact they encode is checked against the sources at the end.
Pentose phosphate pathway mnemonic: oxidize, then shuffle
The same hooks work if your course calls it the HMP shunt. Picture two rooms. The first has a one-way door and pays out NADPH; the second has a revolving door and only rearranges carbons.
Room 1, oxidative (one-way, pays out NADPH):
glucose-6-P → G6PD (NADPH #1) → 6-phosphogluconolactone → lactonase → 6-phosphogluconate → 6-phosphogluconate dehydrogenase (NADPH #2 + CO₂) → ribulose-5-P
Room 2, non-oxidative (revolving door, no NADPH):
ribulose-5-P ⇄ ribose-5-P and xylulose-5-P ⇄ transketolase and transaldolase ⇄ fructose-6-P + glyceraldehyde-3-P
| Hook | What it encodes |
|---|---|
| Oxidize, then shuffle | Oxidative phase first: irreversible, 2 NADPH + 1 CO₂ per glucose-6-P. Non-oxidative phase second: reversible, no NADPH |
| Three Ts | Transketolase needs Thiamine pyrophosphate and moves Two carbons |
| Aldolase = three | Transaldolase moves three carbons, just as glycolytic aldolase splits fructose-1,6-bisphosphate into two three-carbon sugars |
| Build, protect, kill | NADPH builds (fatty acids, cholesterol, steroids, DNA precursors), protects (glutathione) and kills (the respiratory burst) |
| 2 + 2 + 2 + 1 | CPIC's high-risk drugs in G6PD deficiency: two uricases (rasburicase, pegloticase), two 8-aminoquinoline antimalarials (primaquine at standard doses, tafenoquine), two "blues" (methylene blue, toluidine blue), plus dapsone |
| Test after the storm | A G6PD assay can read normal right after hemolysis; retest 2–3 months later |
The carbon counts prove the middle two hooks. Transketolase runs 5C + 5C ⇄ 7C + 3C and 5C + 4C ⇄ 6C + 3C, moving a two-carbon unit each time (UniProt calls it a two-carbon ketol group). Transaldolase runs 7C + 3C ⇄ 4C + 6C, moving a three-carbon (dihydroxyacetone) unit. Net, three pentoses (five-carbon sugars) become two hexoses and one triose, 15 carbons in and 15 out:
Oxidative vs non-oxidative phase: enzymes and products
| Feature | Oxidative phase | Non-oxidative phase |
|---|---|---|
| Direction | Irreversible | Reversible |
| Enzymes | G6PD (committed, rate-limiting step), 6-phosphogluconolactonase, 6-phosphogluconate dehydrogenase | Ribose-5-P isomerase, ribulose-5-P epimerase, transketolase (TPP), transaldolase |
| Converts | Glucose-6-P to ribulose-5-P + CO₂ | Pentose phosphates to and from fructose-6-P and glyceraldehyde-3-P |
| NADPH | 2 per glucose-6-P, one at each dehydrogenase | None |
| Classic exam defect | G6PD deficiency | Thiamine deficiency (low transketolase activity) |
Adding up the three enzyme reactions listed by Expasy gives the oxidative phase in one line (G6P is glucose-6-phosphate; Ru5P is ribulose-5-phosphate):
Because the second room is reversible, the pathway bends to what the cell needs. TeSlaa and colleagues (Nature Metabolism, 2023) describe the modes:
- Needs ribose and NADPH (a dividing cell): the oxidative phase supplies both, and ribose-5-phosphate becomes PRPP, the activated ribose for nucleotide synthesis.
- Needs more ribose than NADPH ("pentose insufficiency"): the non-oxidative steps build ribose-5-P from fructose-6-P and glyceraldehyde-3-P, and no NADPH is made.
- Needs more NADPH than ribose ("pentose overflow" or "pentose cycling"): spare pentoses return to glycolysis, or are recycled into glucose-6-P to run the oxidative phase again. Neutrophils use partial cycling to fuel the oxidative burst.
Rate-limiting step: G6PD and how it is regulated
G6PD oxidizes glucose-6-phosphate to 6-phosphogluconolactone while reducing NADP⁺ to NADPH. Reactome calls it the first committed step of the pathway; exams call it rate-limiting.
- NADP⁺ activates, NADPH inhibits. StatPearls describes allosteric activation by NADP⁺ and inhibition by NADPH. TeSlaa adds that NADP⁺ drives the enzyme both as its substrate and through an allosteric site, so spending NADPH (on glutathione, fat synthesis or the respiratory burst) speeds the pathway up.
- Spare capacity. In most resting cells the pathway carries 10–100 times less flux than glycolysis, but it has reserve capacity that turns on within seconds when oxidant stress raises NADP⁺.
- Diet. G6PD activity rises in the fed state on a high-carbohydrate diet and falls in starvation or diabetes (StatPearls).
- Every cell has it; red cells need it most. G6PD is a housekeeping enzyme, but red cells have no mitochondria and only limited TCA intermediates, which the main alternative NADPH sources (isocitrate dehydrogenase 1 and malic enzyme 1) need. CPIC's guideline puts it bluntly: in red cells, G6PD and 6-phosphogluconate dehydrogenase are the only available source of NADPH.
For how G6PD compares with other control points, see the rate-limiting enzymes table.
What NADPH does, and which tissues run the pathway hardest
NADPH is reducing power for building and for defense. Molecular Biology of the Cell explains the split with NADH: NADPH works chiefly with enzymes of anabolic (building) reactions, while NADH feeds the catabolic reactions that make ATP; the extra phosphate makes the two bind different enzymes.
| Job | Enzyme that spends NADPH | Exam link |
|---|---|---|
| Protect: keep glutathione reduced | Glutathione reductase; reduced glutathione then clears hydrogen peroxide | G6PD deficiency |
| Kill: respiratory burst | NADPH oxidase makes superoxide in phagocytes | Chronic granulomatous disease |
| Kill and signal: nitric oxide | Nitric oxide synthase | Macrophage killing |
| Build: fatty acids, cholesterol, steroids | Reductive biosynthetic enzymes | Liver, adipose tissue, adrenal cortex, lactating breast |
| Build: DNA precursors | Ribonucleotide reductase, via thioredoxin | Dividing cells |
| Detoxify: drug metabolism | Cytochrome P450 enzymes, via NADPH-cytochrome P450 reductase | Liver |
| Rescue: methemoglobin reduction | Methylene blue must first be reduced by an NADPH-dependent reductase | Why methylene blue fails in G6PD deficiency |
Fat synthesis is walked through in the fatty acid synthesis guide, and the sterol route in the cholesterol synthesis pathway.
Tissue distribution. StatPearls lists the adrenal cortex, the mammary gland during milk production and the liver, all with heavy anabolic work, plus red blood cells. That is the exam answer. TeSlaa adds a nuance: G6PD expression is high in the lactating mammary gland and brown fat but not in the liver, which makes NADPH in other ways. Phagocytes switch the pathway on during the oxidative burst.
Transketolase, thiamine and the red-cell transketolase test
Transketolase uses thiamine pyrophosphate (TPP, also called thiamine diphosphate), the active form of vitamin B1; Reactome describes the active enzyme as a dimer with one TPP and one magnesium ion bound to each subunit. TPP is also the cofactor for pyruvate dehydrogenase, α-ketoglutarate dehydrogenase and branched-chain α-ketoacid dehydrogenase, so thiamine deficiency hits energy metabolism and the PPP at once.
The functional test (ETKAC):
- Measure transketolase activity in a red-cell hemolysate with and without added TPP.
- Divide the two: the ratio is the erythrocyte transketolase activity coefficient (ETKAC).
- A big rise means the enzyme was sitting without its cofactor. Jones and colleagues (2021) give the commonly used cutoffs: above 1.25 (a rise of more than 25%) indicates risk of deficiency, 1.15–1.25 a low risk and below 1.15 sufficiency; beriberi usually runs above 1.4. There is no international consensus on cutoffs.
StatPearls notes that whole-blood thiamine diphosphate measured by HPLC reflects tissue stores better than serum thiamine. Either way, results come too slowly to guide the first dose.
Wernicke encephalopathy is the classic thiamine emergency: mental status change, ophthalmoparesis (often with nystagmus) and gait ataxia, with lesions in the mammillary bodies, medial thalami and periaqueductal gray (StatPearls, 2026). Only a minority show all three signs: 16–20% in older autopsy series, about a third in recent pooled analyses (Goldani and colleagues, 2026). Alcohol use disorder is the classic setting, alongside severe malnutrition, hyperemesis gravidarum and bariatric surgery. Untreated, it can progress to Korsakoff syndrome: severe anterograde amnesia, often with confabulation.
Treatment is high-dose parenteral thiamine (UK guidance cited by StatPearls: 500 mg IV every 8 hours for 3 days); oral dosing is not reliable. Give it before or with glucose when you can, but StatPearls is explicit that treating significant hypoglycemia should not wait for thiamine. Clinical detail is in the thiamine, beriberi and Wernicke guide.
G6PD deficiency: X-linked oxidant hemolysis
The G6PD gene sits at Xq28, so males with one deficient allele are G6PD deficient, while heterozygous females range from normal to deficient because of random X inactivation (lyonization). G6PD deficiency affects roughly 400 million (StatPearls) to 500 million (WHO) people, concentrated in the malaria belt: sub-Saharan Africa, the Mediterranean, the Middle East, and South and Southeast Asia. Most never have symptoms.
The hemolysis chain:
oxidant → NADPH falls → glutathione reductase stalls → reduced glutathione runs out → peroxide oxidizes hemoglobin and membrane → denatured hemoglobin precipitates as Heinz bodies → splenic macrophages pit them out (bite cells), and badly damaged cells lyse in the circulation
- Triggers: infection (the most common), fava beans (favism, which can be fatal, mostly in children), oxidant drugs, naphthalene and diabetic ketoacidosis.
- Old cells are the weak point. Unstable G6PD variants lose activity as red cells age, while young cells carry more enzyme. Episodes are usually self-limited once the trigger is gone, and a test during recovery can look normal.
- Both compartments. Splenic removal of bite cells is extravascular hemolysis; severe oxidant injury also causes intravascular hemolysis with hemoglobinuria.
- Newborns. G6PD deficiency raises the risk of neonatal hyperbilirubinemia; in a US registry, about 20% of infants with kernicterus had it. StatPearls summarizes the AAP advice: test G6PD activity in jaundice of unknown cause or bilirubin that rises despite intensive phototherapy; universal US newborn screening is not advised.
- Severity classes. WHO's 2022 classification replaced classes I–V with A (under 20% activity, chronic hemolysis), B (under 45%, triggered acute hemolysis and neonatal jaundice; all the common variants), C (over 60%, no hemolysis) and U (uncertain significance).
Variants, labs and management are covered in the G6PD deficiency guide.
G6PD drug triggers: what current labels say
Classic trigger lists are long, and some still include salicylates and sulfonamides (Merck). The Clinical Pharmacogenetics Implementation Consortium (CPIC) guideline (2023) sorted drugs by strength of evidence, regulatory warnings and mechanism: avoid high-risk drugs, use medium-risk drugs with caution and use low-to-no-risk drugs normally. Current US labels contraindicate rasburicase, pegloticase, tafenoquine and methylene blue in G6PD deficiency and primaquine in severe deficiency, and urge caution with dapsone.
| Drug | Current US label | CPIC risk |
|---|---|---|
| Rasburicase (Elitek) | Boxed warning; contraindicated in G6PD deficiency; screen higher-risk patients (e.g., African or Mediterranean ancestry); hydrogen peroxide is a by-product; severe hemolysis came within 2–4 days of starting. CPIC names allopurinol as the alternative, though it may be less effective | High |
| Pegloticase (Krystexxa) | Boxed warning for G6PD-associated hemolysis and methemoglobinemia; contraindicated; screen at-risk patients | High |
| Primaquine | G6PD testing must be done before use; contraindicated in severe deficiency; in mild to moderate deficiency, weigh risks and monitor hemoglobin (e.g., days 3 and 8) | High at 0.25–0.5 mg/kg daily for 14 days; medium at 0.75 mg/kg weekly for 8 weeks |
| Tafenoquine (Krintafel, Arakoda) | Test every patient; contraindicated with G6PD deficiency or unknown status; long half-life (about 17 days on the Arakoda label), so hemolysis can be delayed | High |
| Dapsone | Dose-related hemolysis occurs with or without G6PD deficiency and is exaggerated with it; give with caution | High |
| Methylene blue (ProvayBlue) | Contraindicated; may not work, because it must be reduced to its active form | High |
| Nitrofurantoin | Warning: hemolytic anemia "of the primaquine-sensitivity type"; stop the drug if it occurs | Medium |
| Sulfamethoxazole (with trimethoprim) | Warning: hemolysis may occur, often dose-related | Low-to-no |
CPIC also rates chloroquine, hydroxychloroquine, quinine, ciprofloxacin, aspirin up to 1 g/day and vitamin C as low-to-no risk, and it found no peer-reviewed evidence for foods other than fava beans. Primaquine and tafenoquine matter most in malaria, where radical cure clears the dormant liver stages of P. vivax and P. ovale.
Heinz bodies, bite cells and when to test for G6PD
During an episode, labs show falling hemoglobin, reticulocytosis, indirect hyperbilirubinemia, high LDH, low haptoglobin and usually a negative direct antiglobulin test (DAT). The routine smear shows bite cells and blister cells. Heinz bodies, clumps of denatured hemoglobin attached to the membrane, need a supravital stain; they are invisible on routine Wright stain. They are not specific: StatPearls also links them to unstable hemoglobins (such as Hb Köln), beta-thalassemia and oxidant drugs such as dapsone.
- Screen vs confirm. The fluorescent spot test is the usual qualitative screen but can miss heterozygous females; a quantitative assay settles female and borderline results (StatPearls).
- Timing. Results can be falsely normal right after hemolysis (the surviving young cells are rich in G6PD) or a transfusion (donor cells are normal). Medical Genetics Summaries advise testing 2–3 months later (Merck says repeat testing may be needed several weeks after the event), and the primaquine label says to postpone the test until recovery from severe anemia.
- Genotyping is reliable in people with one X chromosome; enzyme activity still matters in females (CPIC).
If the episode came with methemoglobinemia (rasburicase and pegloticase can cause both), methylene blue is contraindicated. StatPearls lists alternatives: high-flow oxygen, IV ascorbic acid, transfusion or exchange transfusion, and hyperbaric oxygen in selected cases. The oximetry side of methemoglobinemia is in the oxygen-hemoglobin dissociation curve guide.
Chronic granulomatous disease and other look-alikes
G6PD deficiency is a shortage of NADPH; chronic granulomatous disease (CGD) is a broken consumer of it. NADPH oxidase in phagocytes passes electrons from NADPH to oxygen to make superoxide, which becomes hydrogen peroxide (via superoxide dismutase) and hypochlorous acid (via myeloperoxidase). In CGD one of its subunits fails:
- Genetics: X-linked CYBB (gp91phox) causes about two-thirds of cases; the rest are autosomal recessive, most often NCF1 (p47phox).
- Infections: classically catalase-positive organisms: Staphylococcus aureus, Burkholderia cepacia, Serratia marcescens, Nocardia and Aspergillus.
- Tests: the dihydrorhodamine (DHR) assay measures hydrogen peroxide production; the nitroblue tetrazolium (NBT) slide test measures superoxide.
- Management: lifelong trimethoprim-sulfamethoxazole and itraconazole prophylaxis, interferon-gamma in some countries, and hematopoietic cell transplantation as the only established cure.
The two diseases meet at the extreme: TeSlaa notes that severe G6PD mutations phenocopy CGD, because neutrophils cannot fuel the oxidative burst. More in the chronic granulomatous disease guide.
| Stem clue | Think | What is missing |
|---|---|---|
| Hemolysis after an oxidant (drug, fava beans, infection); bite cells; negative DAT | G6PD deficiency | NADPH, then reduced glutathione |
| Chronic hemolysis and splenomegaly with no trigger; autosomal recessive | Pyruvate kinase deficiency | ATP from glycolysis |
| Recurrent catalase-positive infections and granulomas; abnormal DHR | Chronic granulomatous disease | Superoxide from NADPH oxidase |
| Confusion, ophthalmoplegia, ataxia; transketolase rises with added TPP | Thiamine deficiency | TPP for transketolase and the dehydrogenases |
| Hemolysis plus methemoglobinemia after rasburicase or pegloticase | G6PD deficiency | NADPH to clear hydrogen peroxide |
USMLE traps: classic teaching vs current evidence
| Trap | What's actually true |
|---|---|
| "Most directly decreased" in G6PD deficiency is glutathione | NADPH falls first; reduced glutathione falls one step later |
| A normal G6PD level during hemolysis rules it out | Young cells and transfused cells can mask it; retest 2–3 months later |
| Only males are affected | Heterozygous females can be deficient through lyonization, and spot tests can miss them |
| Sulfa drugs are a top G6PD trigger | CPIC rates sulfamethoxazole low-to-no risk (weak evidence), though the Bactrim label still warns; CPIC's high-risk list is dapsone, methylene blue, pegloticase, standard-dose primaquine, rasburicase, tafenoquine and toluidine blue |
| WHO classes I–V | Replaced in 2022 by A, B, C and U; former classes II and III merged into B |
| Always give thiamine before glucose | Give it before or with glucose, but never delay treating hypoglycemia; a 2012 review found no evidence for the old rule beyond case reports |
| Wernicke needs the full triad | A minority: 16–20% in older autopsy series, about a third in recent pooled analyses; treat on suspicion |
| G6PD deficiency protects against severe malaria | Sources differ: TeSlaa describes protection from severe malaria, while StatPearls reports partial protection against uncomplicated malaria and uncertain protection against severe malaria in pooled analyses |
| NADH and NADPH are interchangeable | The extra phosphate makes them bind different enzymes: NADPH serves biosynthesis and antioxidant defense, NADH mainly ATP-generating catabolism |
| Erythrose-4-phosphate makes aromatic amino acids | Only in microbes and plants; in humans phenylalanine and tryptophan are dietary essentials |
| Ribose-5-phosphate matters in a red-cell question | Mature red cells have no nucleus and make no DNA; the crisis is about NADPH |
Practice vignettes
Vignette 1: hemolysis two days after rasburicase. A 58-year-old man of West African ancestry with newly diagnosed high-grade lymphoma receives rasburicase before chemotherapy; nobody checked his G6PD status. Two days later he has dark urine and scleral icterus. Hemoglobin has fallen from 13 to 8 g/dL, LDH is high, haptoglobin is undetectable and the DAT is negative. He is cyanotic despite supplemental oxygen, and his methemoglobin level is raised. The mechanism: rasburicase converts uric acid to allantoin and releases hydrogen peroxide, and his red cells cannot make enough NADPH to keep glutathione reduced. Stop rasburicase permanently and support him with transfusion. The tempting wrong moves are giving methylene blue (contraindicated, and it needs NADPH to work) and trusting a normal G6PD result drawn this week (retest in 2–3 months). A negative DAT argues against autoimmune hemolysis.
Vignette 2: confusion, nystagmus and a low glucose. A 46-year-old man with alcohol use disorder is found confused and unsteady. He has horizontal nystagmus, bilateral lateral rectus weakness and a wide-based gait; fingerstick glucose is 48 mg/dL. Give IV thiamine and dextrose together; holding the dextrose until thiamine arrives is the outdated move. A red-cell transketolase assay drawn before treatment returns days later with an ETKAC of 1.32: activity rose 32% when TPP was added, so the enzyme had been short of its cofactor. The result confirms thiamine deficiency but should never delay treatment. Low transketolase activity points to the non-oxidative PPP, not to G6PD.
Key takeaways
- Oxidize, then shuffle: the oxidative phase is irreversible and makes 2 NADPH + 1 CO₂ per glucose-6-P; the non-oxidative phase is reversible and makes none.
- G6PD catalyzes the committed, rate-limiting step; NADP⁺ activates it and NADPH inhibits it.
- Three Ts: transketolase needs thiamine (TPP) and moves two carbons; transaldolase moves three. An ETKAC above 1.25 suggests thiamine deficiency.
- NADPH builds, protects and kills: fatty acid, cholesterol and steroid synthesis; glutathione reduction; the respiratory burst.
- G6PD deficiency is X-linked oxidant hemolysis with bite cells and Heinz bodies; avoid rasburicase, pegloticase, tafenoquine, methylene blue, dapsone and standard-dose primaquine, and retest 2–3 months after an episode.
- CGD is a broken NADPH oxidase, not an NADPH shortage.
More pathway walkthroughs are on the Biochemistry hub.
Sources
- Biochemistry, Hexose Monophosphate Pathway — StatPearls (2023)
- TeSlaa T, Ralser M, Fan J, Rabinowitz JD. The pentose phosphate pathway in health and disease — Nature Metabolism (2023)
- Pentose phosphate pathway — Reactome
- Glucose-6-phosphate dehydrogenase, EC 1.1.1.49 — Expasy ENZYME
- 6-Phosphogluconolactonase, EC 3.1.1.31 — Expasy ENZYME
- Phosphogluconate dehydrogenase, EC 1.1.1.44 — Expasy ENZYME
- Transketolase, EC 2.2.1.1 — Expasy ENZYME
- Transaldolase, EC 2.2.1.2 — Expasy ENZYME
- Fructose-bisphosphate aldolase, EC 4.1.2.13 — Expasy ENZYME
- Transketolase (TKT), human — UniProt P29401
- Lane AN, Fan TW-M. Regulation of mammalian nucleotide metabolism and biosynthesis — Nucleic Acids Research (2015)
- Catalysis and the Use of Energy by Cells — Molecular Biology of the Cell, 4th ed. (2002)
- Glucose-6-Phosphate Dehydrogenase Deficiency — StatPearls (2025)
- Heinz Body — StatPearls (2026)
- Glucose-6-Phosphate Dehydrogenase (G6PD) Deficiency — Merck Manual Professional Edition (2026)
- Biochemistry, Essential Amino Acids (archived) — StatPearls
- Gammal RS, et al. Expanded CPIC Guideline for Medication Use in the Context of G6PD Genotype — Clinical Pharmacology & Therapeutics (2023)
- Luzzatto L, et al. New WHO classification of genetic variants causing G6PD deficiency — Bulletin of the World Health Organization (2024)
- Rasburicase Therapy and G6PD and CYB5R Genotype — Medical Genetics Summaries (2026)
- Primaquine Therapy and G6PD and CYP2D6 Genotype — Medical Genetics Summaries (2026)
- Tafenoquine Therapy and G6PD Genotype — Medical Genetics Summaries (2026)
- Elitek (rasburicase) Label — DailyMed (2026)
- Krystexxa (pegloticase) Label — DailyMed (2026)
- Primaquine Phosphate Tablets Label — DailyMed (2026)
- Krintafel (tafenoquine) Label — DailyMed (2023)
- Arakoda (tafenoquine) Label — DailyMed (2025)
- Dapsone Tablets Label — DailyMed (2026)
- ProvayBlue (methylene blue) Label — DailyMed (2025)
- Macrobid (nitrofurantoin) Label — DailyMed (2025)
- Bactrim (sulfamethoxazole and trimethoprim) Label — DailyMed (2024)
- Methylene Blue — StatPearls (2026)
- Vitamin B1 (Thiamine) Deficiency — StatPearls (2026)
- Wernicke-Korsakoff Syndrome — StatPearls (2026)
- Goldani AAS, et al. Undertreatment of Wernicke encephalopathy: a scoping review — Addiction Science & Clinical Practice (2026)
- Jones KS, et al. Erythrocyte transketolase activity coefficient (ETKAC) assay protocol for the assessment of thiamine status — Annals of the New York Academy of Sciences (2021)
- Schabelman E, Kuo D. Glucose before thiamine for Wernicke encephalopathy: a literature review — Journal of Emergency Medicine (2012)
- Chronic Granulomatous Disease — StatPearls (2022)
- Arnold DE, Heimall JR. A Review of Chronic Granulomatous Disease — Advances in Therapy (2017)
- Pyruvate kinase deficiency — MedlinePlus Genetics
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
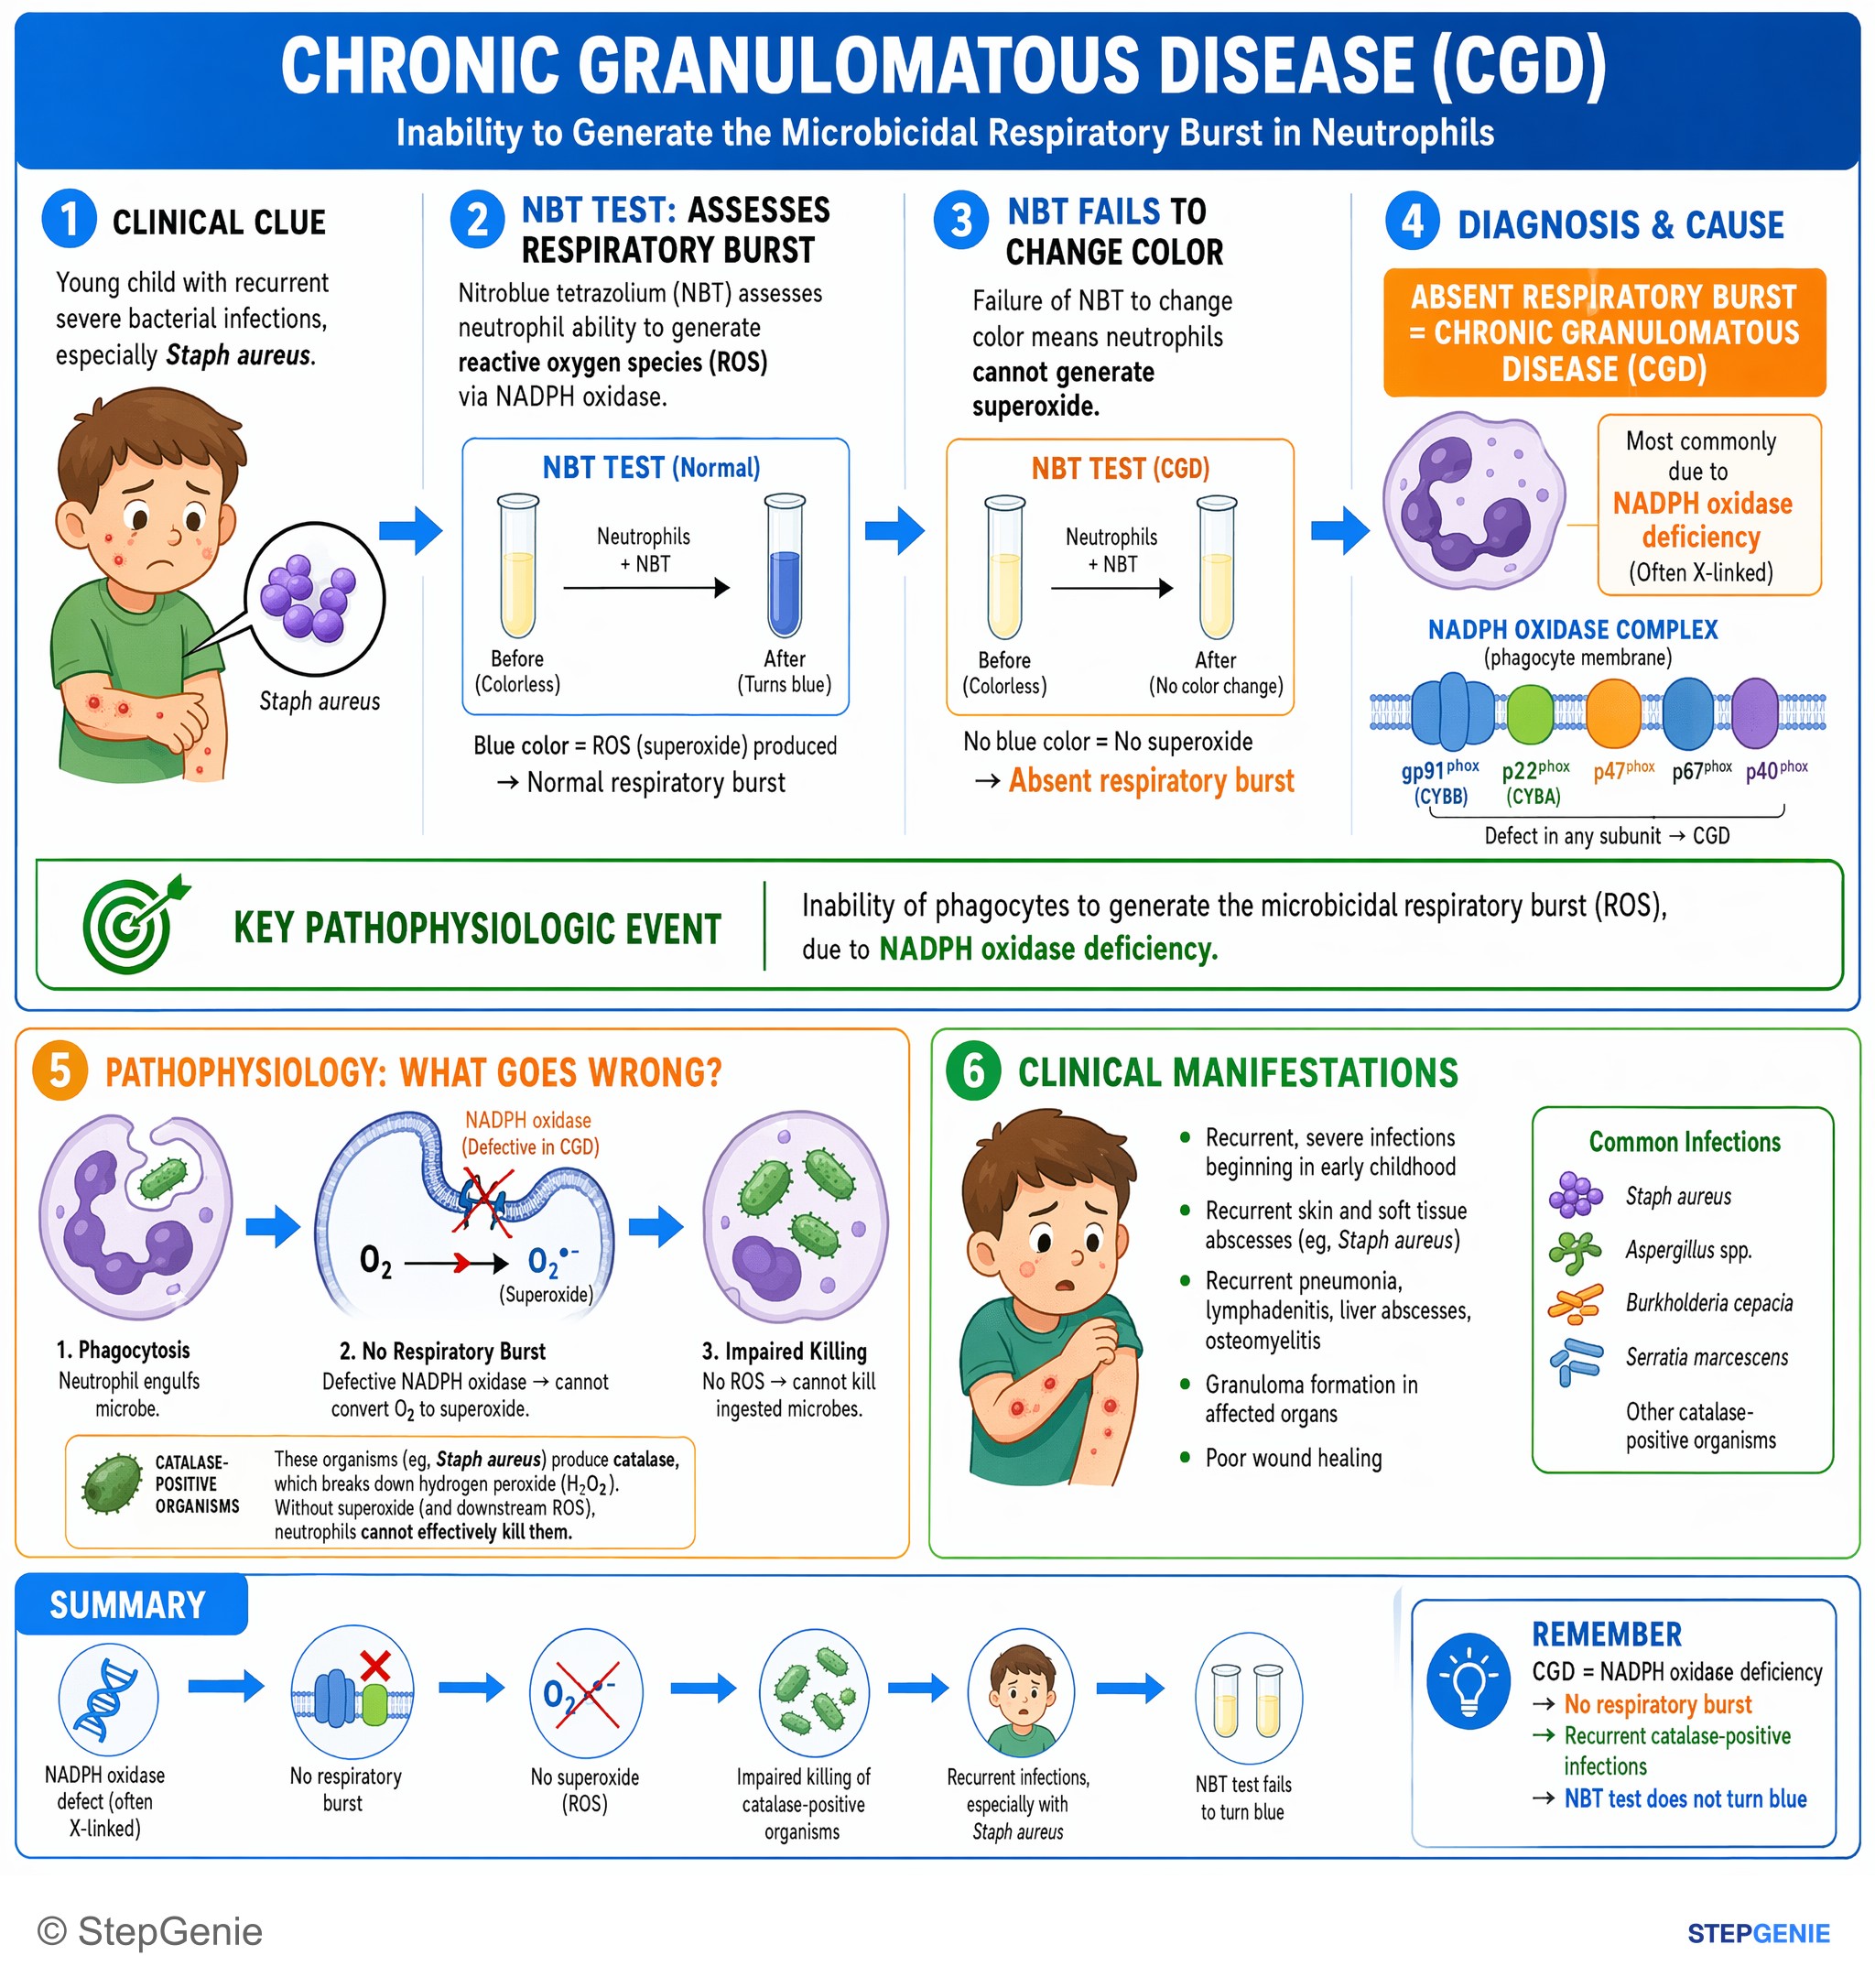
Chronic granulomatous disease: NADPH oxidase defect → no respiratory burst → recurrent catalase-positive infections; NBT test fails to…
USMLE Step 1Frequently Asked Questions
What is a good mnemonic for the pentose phosphate pathway?
Use "oxidize, then shuffle." The oxidative phase comes first, is irreversible and makes 2 NADPH and 1 CO2 per glucose-6-phosphate, with G6PD as the rate-limiting enzyme. The non-oxidative phase comes second, is reversible and only rearranges sugar carbons, so it makes no NADPH. Then add "three Ts": transketolase needs thiamine and transfers two carbons, while transaldolase transfers three, the way glycolytic aldolase splits a sugar into three-carbon halves.
What is the rate-limiting step of the pentose phosphate pathway?
The first step, catalyzed by glucose-6-phosphate dehydrogenase (G6PD), which oxidizes glucose-6-phosphate to 6-phosphogluconolactone and reduces NADP+ to NADPH. It is the committed step. NADP+ activates the enzyme and NADPH inhibits it, so the pathway speeds up whenever a cell spends NADPH, for example on glutathione during oxidant stress. Inherited G6PD deficiency is X-linked and leaves red cells short of NADPH, so they hemolyze under oxidant stress.
How many NADPH are produced in the pentose phosphate pathway?
Two NADPH per glucose-6-phosphate, both in the oxidative phase: one from G6PD and one from 6-phosphogluconate dehydrogenase, which also releases CO2 and forms ribulose-5-phosphate. The non-oxidative phase makes none; it only interconverts pentoses with fructose-6-phosphate and glyceraldehyde-3-phosphate. A cell that needs extra NADPH can recycle those products back to glucose-6-phosphate and run the oxidative phase again, which neutrophils do in part during the oxidative burst.
What is the pentose phosphate pathway used for?
It makes two things. Ribose-5-phosphate becomes PRPP for nucleotide synthesis. NADPH builds fatty acids, cholesterol, steroids and DNA precursors, protects cells by keeping glutathione reduced, and powers the phagocyte respiratory burst through NADPH oxidase. The pathway runs in the cytosol. Classic exam lists of high-activity tissues name the liver, adrenal cortex, lactating mammary gland and red cells, and red cells depend on it most because they lack mitochondria.
Which pentose phosphate pathway enzyme needs thiamine?
Transketolase, in the non-oxidative phase, needs thiamine pyrophosphate (thiamine diphosphate), the active form of vitamin B1. That is the basis of the erythrocyte transketolase activity coefficient: activity is measured with and without added thiamine pyrophosphate, and a ratio above 1.25, a rise of more than 25%, indicates risk of deficiency. Wernicke encephalopathy is still treated on clinical suspicion with IV thiamine, without waiting for the result.
Which drugs should be avoided in G6PD deficiency?
The 2023 CPIC guideline rates dapsone, methylene blue, pegloticase, primaquine at standard doses, rasburicase, tafenoquine and toluidine blue as high risk, and nitrofurantoin as medium risk. US labels contraindicate rasburicase, pegloticase, methylene blue and tafenoquine in G6PD deficiency, and primaquine in severe deficiency. Sulfamethoxazole, the classic sulfa example, is rated low-to-no risk by CPIC, though its label still warns of dose-related hemolysis.